

Waking at 3AM with anxiety can happen when stress, worry or broken sleep keeps your mind too alert to settle. The hour alone can’t tell you the cause. If you wake up at 3AM with anxiety, try not to watch the clock or force sleep. If it keeps happening or hurts your days, ask a clinician.
Based on NHLBI and NHS guidance · What to do tonight, step by step

It’s 3AM. You were asleep a while ago, and now your mind is wide awake. Many people who wake up at 3AM with anxiety describe the same spiral: tomorrow will be ruined, or what’s wrong with me?
Waking during the night is a recognized sign of insomnia. For chronic insomnia, the 2025 VA/DoD guideline gives CBT-I, a structured treatment, a strong recommendation. That means you have somewhere to go from here.
This guide covers what to do tonight, why waking like this happens, how to tell worry from panic, and when to get help. It sits inside our Mental Health & Sleep library.
Not sure which part applies to you? The 3AM anxiety Sleep Compass points you to your starting point in about a minute.
Is this you? Pick the line that sounds like your night.
- “Tomorrow will be ruined.” → how worry about lost sleep builds.
- “My brain is wide awake.” → a calm sequence for tonight.
- “Now I kind of expect it.” → how that loop feeds itself.
- “I’m doing everything right.” → what structured treatment adds.
These are things people say about nights like this. They describe a feeling, not a diagnosis.
This guide explains waking at 3AM with anxiety for general education. It can’t diagnose you or replace care from a clinician who knows your health.
What Should You Do If You Wake Up Anxious at 3AM?
You’re awake, your mind is racing, and the night feels long. Start by looking away from the clock and not forcing sleep. Watching the clock and worrying about sleep can make insomnia worse. First, check whether anything feels urgent. Then try the steps below, which draw on NHS and CBT-I advice.
Many people in this spot ask what’s wrong with me? Waking several times in the night is a recognized sign of insomnia (NHS, 2024). That gives the problem a name, and a name gives you somewhere to start.
Tonight’s steps
A calm sequence for a 3AM awakening
- Scan for urgent signs — If you have thoughts of suicide or self-harm, or you feel in danger, go to the urgent-help steps now. Severe or unexplained physical symptoms need medical care, not a guess that it’s anxiety.
- Leave the clock alone — Turn it away if you can. Clock-watching and worry about sleep can raise the risk of insomnia, according to NHLBI.
- Don’t force sleep — Give yourself permission not to fall asleep right now. Rest quietly instead of fighting the night.
- Get up if you stay awake — CBT-I advice is to go to bed only when sleepy and to get out of bed if you can’t sleep. Do something quiet and safe, then return when sleepy. If you have a fall risk or trouble getting in or out of bed, ask a clinician how to adapt this step.
- Keep your usual wake time — The NHS advises getting out of bed at the same time every day. Aim for that tomorrow too.
None of this promises sleep. It helps you stop fighting the night, and that is the part you control.
In the morning, the sleep diary to record awakenings and prepare for appointments is a simple place to note what happened.
For gentle ways to settle, our sleep meditation techniques guide covers calming practices for bedtime and waking.
Why Do I Wake Up at 3AM with Anxiety?
Stress, worry, anxiety, sleep changes and your bedroom can all contribute to waking at night. Caffeine, alcohol and other health issues can too. The 3AM hour itself can’t tell you which one applies. So the useful question is not “why 3AM?” but “what is feeding my wakefulness?”
Waking up at 3AM anxious can feel random. It can involve more than one cause. Stress or worry about work, relationships or money raises the risk of insomnia (NHLBI, 2022). The NHS also lists anxiety and depression. Caffeine and alcohol can add to it.
None of the guidance used for this page treats 3AM as a special hour. You can stop searching for a secret meaning in the number.
“Waking at exactly 3AM means my cortisol is dangerously high.”
The hour alone doesn’t show your cortisol level. Anxiety, sleep disruption and other contributors all matter, so a hormone cause shouldn’t be assumed.
“I fall asleep easily, so it can’t be insomnia.”
Insomnia can mean waking several times in the night, or waking early and not getting back to sleep.
So the 3AM hour doesn’t point to one cause. If the cortisol idea worries you, a separate guide goes deeper into how cortisol and sleep disruption connect.
To see how all these contributors fit together, the wake up at 3AM with anxiety mind map lays out the whole picture on one page.
Is It Nighttime Panic or Anxious Thinking?
A panic attack brings a rush of intense mental and physical symptoms. Anxious thinking is more about worry and a busy mind. Waking anxious can’t, on its own, tell you which one happened. Some physical problems can feel similar. That’s why patterns and an assessment matter more than a guess.
The NHS describes panic as a sudden rush of symptoms, sometimes with no obvious reason (NHS, undated). The table shows broad differences only. It can’t sort out your own night.
| What you notice | What it might point to | What matters next |
|---|---|---|
| A busy mind and worry about sleep | Stress, worry and clock-watching can feed insomnia. | Break the worry-and-clock habit, as in the steps above. |
| A sudden rush of intense body and mind symptoms | A panic attack is one possibility. | Symptoms alone don’t confirm panic disorder or rule out illness. A clinician can assess. |
| Snoring, gasping or choking when you wake | A sleep breathing problem is possible. | Ask about assessment. A sleep clinic referral may follow. |
In plain terms, a worried mind and a panic surge can look alike at 3AM. The details you notice are worth writing down.
If sudden, intense surges are what wake you, the nighttime panic attacks guide follows that pattern in depth.
If a racing heart is your main symptom, our questions page compares panic and breathing problems as possible explanations, without diagnosing either.
Why Do Racing Thoughts Keep You Awake?
Stress and worry can disturb sleep. Then worry about losing sleep can make your mind more alert. Checking the clock adds fuel. Together, these can worsen insomnia and deepen your concern about the next night. That is the loop behind the thought now I kind of expect it.

CBT-I can target this loop. It addresses a busy or racing mind and inaccurate sleep-related thoughts (VA/DOD, 2025). It is a treatment for chronic insomnia, not a quick fix for one night.
You can start small. Next time you wake, notice the urge to check the clock. Leave it alone and tell yourself: that’s worry talking. Stop and get up if you’re still wide awake.
Worry that starts before bed can follow you into the night. Our guide to bedtime worry that continues into the night covers that side.
The stress-insomnia cycle guide shows how sleep worry feeds more wakefulness.
When Does Nighttime Waking Become Insomnia?
Waking at night is a symptom. Chronic insomnia disorder means sleep trouble at least three times a week for more than three months. Other requirements apply, such as daytime effects and ruling out other causes. One rough night doesn’t make a disorder.
The 2025 VA/DoD guideline sets that line. It is a diagnostic threshold, not a measure of how common waking is. Only a clinician can apply it to you.
You don’t need to wait three months to ask for help. The NHS says to see a GP if insomnia makes daily life hard to cope with. The signs that call for help are laid out below.
How often does waking at 3AM with anxiety actually happen? We found no reliable count. Figures for insomnia in general measure something else. Our statistics page shows every figure, with who it applies to.
For a deeper look at assessment and care, our insomnia guide explains how assessment and treatment work.
At a glance
- Night waking — It can be a sign of insomnia, including waking too early.
- Clock-watching — It and sleep worry can make the problem worse.
- Treatment — Chronic insomnia has a strongly recommended option, CBT-I.
- Daytime impact — Trouble coping in daily life deserves an assessment.
- Safety — Some behavioral treatments need adapting to your health.
What Other Problems Could Wake You at Night?
If you keep waking up at 3AM anxious, anxiety may not be the only reason. Sleep breathing problems, pain, restless legs, menopause and thyroid problems can also disturb sleep. So can caffeine, alcohol and your sleep environment. A clock time can’t tell them apart. If one sounds familiar, raise it with a clinician.
- Breathing problems in sleep. Snoring, gasping or choking on waking, or daytime sleepiness, can prompt an assessment.
- Long-term pain. The NHS lists it among possible causes.
- Restless legs. A separate guide looks at leg discomfort that interferes with sleep.
- Menopause. Another factor on the NHS list.
- Overactive thyroid. Also on that list, and a clinician can check it.
- Caffeine, alcohol and nicotine. They can feed insomnia, depending on your own habits.
These are possible contributors, not an explanation for you. Two or more can overlap. Tell a clinician about any medicine you take.
If snoring or gasping sounds familiar, our sleep apnea guide covers the signs and the assessment route. Don’t try to diagnose it yourself.
What Can You Do Tomorrow to Support Better Sleep?
Tomorrow, keep a regular wake time, look at your caffeine and alcohol, and start a simple sleep record. These steps are low-effort and show you your pattern. They may not be enough alone for chronic insomnia. But they help you pick a next step with a clinician.
- Keep a steady wake-up time. The NHS advises going to bed only when sleepy and getting up at the same time every day.
- Look at caffeine and alcohol. Both are recognized contributors. Our guide to caffeine timing for sleep shows one change you can control.
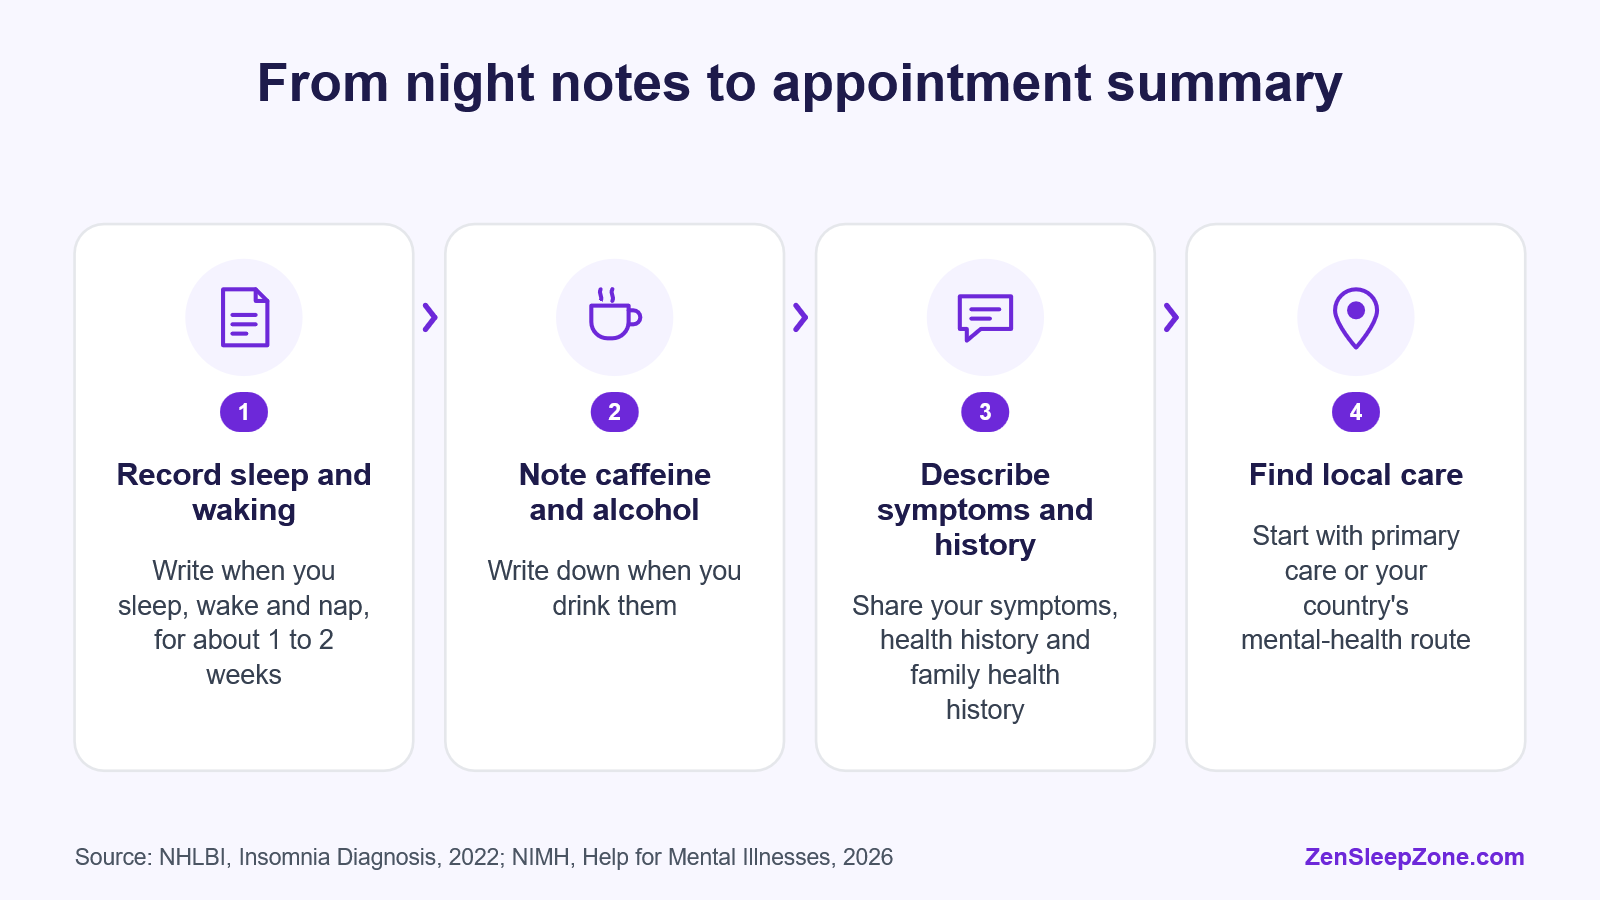
- Start the record. Write down when you go to sleep, wake up and nap each day (NHLBI, 2022). Keep it for 1 to 2 weeks before seeing a doctor.
Picture an adult who sleeps normally at bedtime but wakes with racing thoughts, checks the clock and worries about work. They stop checking the clock and keep a sleep diary. They ask for medical advice if sleep keeps affecting their days.
Alcohol can break up sleep too. Read about alcohol and repeated nighttime waking if you drink in the evening.
Small steps matter, and you don’t have to build the record alone. The sleep diary to record awakenings and prepare for appointments gives you a place to start.
Did you know?
The 2025 VA/DoD guideline suggests against using sleep hygiene education as the only treatment for chronic insomnia. Good habits can still be part of CBT-I. See the CBT-I figures, with who they apply to
What Treatments Help if It Keeps Happening?
For chronic insomnia, the 2025 VA/DoD guideline gives CBT-I a strong recommendation. CBT-I is a structured treatment that works on sleep thoughts and habits. It usually runs 6 to 8 weeks. Medicines are a different decision made with a clinician.
The Veterans Health Administration video below shows what CBT-I involves and how it differs from generic bedtime tips.
Introduction to Cognitive Behavioral Therapy for Insomnia — Veterans Health Administration
How well does it work? A 2015 review pooled 22 trials of adults who had insomnia plus a psychiatric or medical condition (Wu et al., 2015). After treatment, 36% of people who had CBT-I were in remission. In the comparison groups, 16.9% were. That is a bit more than 1 in 3 against about 1 in 6.
In all, 539 people had CBT-I and 482 were in comparison groups. CBT-I had 3.28 times the odds of remission. Trials counted remission in their own ways.
These are group results from adults with other conditions. They can’t predict your own result. They also don’t measure waking at 3AM with anxiety.
CBT-I for chronic insomnia
CBT-I works on sleep-related thoughts and habits, including a busy or racing mind. The 2025 VA/DoD guideline gives it a strong recommendation for chronic insomnia, with moderate confidence in key outcomes.
Expect a course of weeks, not a fix in one night. Some people need it adapted, as listed below.
CBT-I isn’t right to start on your own in every situation. The 2025 VA/DoD guideline lists nine situations that need adapting or delaying CBT-I. If one fits, talk to a clinician first.
- Medically unstable condition. Delay or adapt supervised CBT-I as your clinician directs.
- Active alcohol or drug use disorder. A clinician reviews it before CBT-I starts.
- Excessive daytime sleepiness. A clinician supervises changes or delays treatment.
- Nighttime fall risk or trouble getting in or out of bed. The bed-exit step is adapted with a clinician.
- Ongoing exposure-based PTSD treatment. Discuss timing with your treating clinicians.
- Uncontrolled seizure disorder. Behavioral treatment is delayed or adapted under supervision.
- Bipolar disorder. A clinician leads the adaptation and watches your mood.
- Current acute mental-health symptoms. Urgent symptoms need assessment first. A clinician may advise delaying the program.
- Pregnancy or postpartum insomnia. Discuss a tailored plan with an appropriate clinician.
The guideline suggests CBT-I over medication as the first treatment. That is a softer “suggests,” not a strong “recommends.” The NHS says some sleep products have side effects and to check with a doctor first. The guideline found too little evidence to recommend for or against magnesium.
For session-level detail, our CBT-I guide explains what treatment involves.
When Should You Seek Medical or Urgent Help?
Help comes at two speeds. See a clinician for a routine assessment if sleep trouble lasts for months. The same goes if it makes daily life hard to cope with, or comes with snoring or breathing pauses. Get urgent help now for thoughts of suicide or self-harm, or immediate danger.
Book a routine visit if…
- Daily life is harder. The NHS says to see a GP when insomnia makes it hard to cope.
- It has lasted months. Trouble sleeping for months is a reason to see a primary-care clinician.
- You snore, gasp or stop breathing in sleep. Suspected sleep apnea can lead to a sleep clinic referral.
- Drowsiness makes driving unsafe. Don’t drive when you feel sleepy.
Get urgent help now if…
- You have thoughts of suicide or self-harm. In the US, call or text 988 (988 Lifeline). In Canada, call or text 988 (Public Health Agency of Canada).
- You or someone else is in immediate danger. In the US or Canada, call 911. Elsewhere, call your local emergency number.
- You have severe or unexplained physical symptoms. Get medical care. Panic-like symptoms alone can’t rule out illness.
You now know which level fits your situation. If you’re unsure, start with the routine visit and tell the clinician everything.
How Can You Find Help and Prepare for an Appointment?
Start with a primary-care clinician or a trained sleep or mental-health provider. Routes differ by country. Before you go, keep a sleep diary for 1 to 2 weeks if you can, and write down your questions. That helps a clinician see your pattern.
| Where | Possible route | Worth knowing |
|---|---|---|
| United States | A doctor, nurse or therapist can deliver CBT-I, face to face, by phone or online. | Check coverage with your insurer and look up local providers. |
| United Kingdom | NHS talking therapies for anxiety and depression accept self-referral. Some services accept direct referral for insomnia. | Eligibility and CBT-I availability vary by local service. |
| Canada | A trained clinician such as a psychologist can give tailored CBT-I. Online CBT-I is an option if that isn’t available. | Availability differs by region. |
The UK route comes from NHS guidance (NHS, undated) and CNWL Talking Therapies. Canada’s comes from clinical guidance (CAMH, 2019). If you live elsewhere, start with your primary-care clinician and ask about CBT-I.
A clinician may look for underlying causes. They may refer you to a sleep clinic if another sleep disorder is suspected. CBT-I is described as a 6 to 8 week plan by NHLBI. CAMH says it usually takes three to six sessions. Those are two ways of counting the same kind of care.
- Bring your diary. It shows sleep times, awakenings, naps, caffeine and alcohol.
- Describe your days. Say how the lost sleep affects how you cope.
- Ask about causes. “Could something else be affecting my sleep?”
- Ask about CBT-I. “Is it available to me, and is it safe for my health?”
Questions pile up before a visit. Longer follow-ups, such as why waking can happen later in the night, are answered on our questions page.
For wider links between mood and sleep, our mental health and sleep guide covers assessment and support.
How Can You Track Progress Without Watching the Clock?
Track patterns in the morning, not in the dark. A diary records when you slept, woke and napped, plus how your day felt. It can guide a clinician, but it can’t diagnose you. Keep the clock turned away at night and fill in the details after you get up.
- Bedtime and sleep. When you went to bed and about when you fell asleep.
- Awakenings. When you woke and roughly how long you stayed awake.
- Getting up. The time you finally got out of bed.
- In your own words. What the awakening felt like.
- Habits. Naps, caffeine, alcohol and exercise.
- Your day. Sleepiness and how well you coped.
What if the steps stop working? If your record shows the same pattern after a week or two, or days keep getting harder, take it to a clinician. That’s the moment to ask about CBT-I.
Record your nights in a sleep diaryA sleep diary to record awakenings and prepare for appointments.To see how the pieces connect before your visit, the mind map shows possible contributors and next steps on one page.
Key takeaways
- Remember — Waking at 3AM with anxiety has several possible causes, and the hour alone doesn’t name one.
- Do — Look away from the clock, don’t force sleep and start a simple sleep record.
- If it continues — See a clinician if it lasts or hurts your days, and ask about CBT-I. Get urgent help in a crisis.
You can now pick your next step
Not sure where to begin? The 3AM anxiety Sleep Compass sorts your situation into a starting point. More in Mental Health & Sleep.
Find your starting point →Frequently Asked Questions
Is waking with anxiety always panic disorder?
No. Waking with anxiety does not by itself mean panic disorder. Panic disorder involves recurring panic symptoms and needs a professional assessment. A single anxious awakening can reflect stress, worry, broken sleep or another health issue, and it can’t be sorted out from the symptom alone.
Panic attacks bring a rush of intense mental and physical symptoms. If sudden surges wake you again and again, write down what happens and bring the notes to a clinician. Our guide to nighttime panic attacks describes that pattern in more depth.
What if I cannot fall asleep again tonight?
One hard night doesn’t make a disorder. If you can’t fall back asleep tonight, stay calm, keep the clock turned away and avoid driving while sleepy. Rest quietly, or get up and do something calm until sleepy. Seek assessment if the problem keeps happening or affects how you cope.
A bad night can bring fear about tomorrow. Try to keep your usual wake time anyway, as the NHS advises. Tomorrow you can start a sleep record and look at caffeine and alcohol. The step-by-step plan above works for any night you wake.
Does melatonin stop 3am anxiety awakenings?
We can’t say melatonin will stop 3AM anxiety awakenings. The sources behind this guide don’t test it for that. The 2025 VA/DoD guideline suggests CBT-I over medication as the first treatment for chronic insomnia. The NHS advises checking with a doctor before you take sleep products, as some have side effects.
If you’ve already tried melatonin without luck, tell a clinician. The right plan depends on the cause. The guideline also found too little evidence to recommend for or against magnesium. Our CBT-I guide covers the treatment it recommends for chronic insomnia.
Can caffeine or alcohol contribute to waking?
Yes, caffeine and alcohol can contribute to insomnia. The NHS lists both as possible contributors, along with anxiety and depression. How much they matter depends on your own habits and circumstances. They are one piece of the picture, not a full explanation.
A sleep diary helps you spot a link. Note what you drink and when you wake, then look for a pattern. Our coffee timing guide covers caffeine. A separate alcohol and sleep guide covers repeated waking.
Can I treat recurring insomnia with sleep hygiene alone?
Healthy sleep habits can help, but the 2025 VA/DoD guideline suggests against using sleep hygiene education as the only treatment for chronic insomnia. Habits such as a steady wake time still have a place. For chronic insomnia, the guideline recommends CBT-I, which can include those habits.
The NHS’s public advice and the guideline don’t clash. Self-care can support sleep, while chronic insomnia deserves more specific treatment. Tomorrow’s plan above lists habits worth reviewing, and the treatment section shows what a structured option adds.
Are sleep medications the first treatment for chronic insomnia?
The 2025 VA/DoD guideline suggests CBT-I over medication as the first treatment for chronic insomnia. That is a softer “suggests,” not a firm rule. Medicines can have side effects, and the NHS advises checking with a doctor before taking sleep products. A clinician who knows your health should guide that choice.
“Suggests over” doesn’t mean medicine is off the table. Behavioral treatment comes first, and drug choices are individual. If you want to compare options, bring your diary and a list of your medicines to your visit. The appointment section shows how to prepare.
Can I begin sleep restriction on my own?
Sleep restriction, a supervised approach that changes your time in bed, is best started with a clinician. It is part of some structured insomnia treatments. Medical and safety factors can require adapting or delaying it. The 2025 VA/DoD guideline lists factors such as bipolar disorder or excessive daytime sleepiness.
The full list of nine adaptation situations is in the treatment section above. Bring it to your visit, and ask how CBT-I would be adapted for you. If you have a fall risk at night, say so, because bed-exit steps may need changing.
Sources
- VA/DOD, Clinical Practice Guideline, 2025. Supports: the CBT-I recommendation, the position on sleep hygiene alone, CBT-I over medication, magnesium, racing-thought targets, the chronic insomnia threshold and the nine adaptation situations.
- Wu et al., JAMA Internal Medicine, 2015 (DOI: 10.1001/jamainternmed.2015.3006). Supports: remission rates, group sizes and the pooled odds ratio for CBT-I.
- NHLBI, Insomnia Causes and Risk Factors, 2022. Supports: stress, worry and clock-watching as risk factors.
- NHLBI, Insomnia Treatment, 2022. Supports: leaving bed when you can’t sleep, CBT-I format and its 6 to 8 week length, and US access routes.
- NHLBI, Insomnia Diagnosis, 2022. Supports: what a sleep diary records and keeping one for 1 to 2 weeks.
- NHS, Insomnia, 2024. Supports: symptoms, self-care habits, possible causes, side effects of sleep products, driving safety and when to see a GP.
- NHS, Panic Disorder, undated. Supports: how a panic attack feels.
- NHS, Cognitive Behavioural Therapy, undated. Supports: UK self-referral to talking therapies.
- Public Health Agency of Canada, Suicide Prevention, undated. Supports: the Canadian 988 line and 911 for immediate danger.
- 988 Lifeline, Get Help, undated. Supports: US crisis support by call or text and 911 for emergencies.
- CAMH, Sleep Disorders: Treatment, 2019. Supports: Canadian CBT-I routes and the usual number of sessions.
- CNWL Talking Therapies, Insomnia, undated. Supports: online self-referral to one UK service.
Sources checked · Next review
How we made this guide: researched from the sources above, drafted with AI assistance and edited by Aamir Bashir, Founder & Editor. Read our editorial policy.



