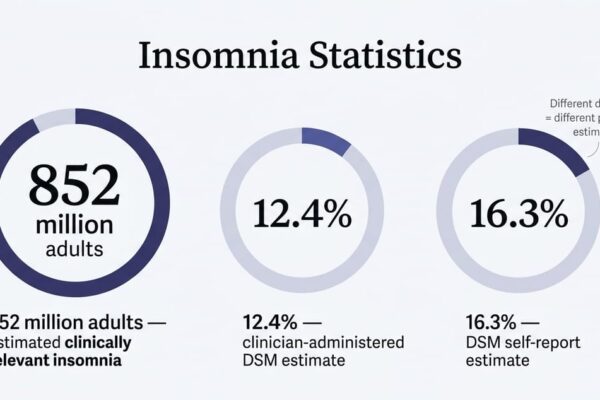
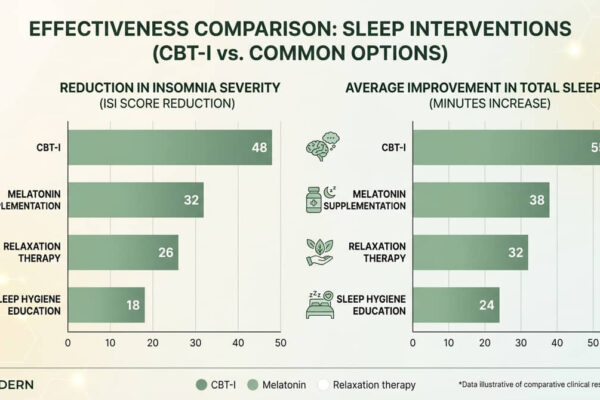
CBT-I for insomnia statistics: the key numbers
CBT-I for insomnia helps people fall asleep about 19 minutes faster and spend about 26 fewer minutes awake at night. That comes from a review of 20 trials with 1,162 adults. Over the longer term, about 4 in 10 people who start with CBT-I are in remission, compared with about 3 in 10 who start with sleep medicine.
- 19.03 minutes faster to fall asleep than control groups, at the end of treatment (Trauer et al., Annals of Internal Medicine, 2015)
- 41% vs 28% in remission at long-term follow-up, starting with CBT-I vs starting with medicine (estimated) (Furukawa et al., Psychiatry and Clinical Neurosciences, 2024)
- About 14% of people in everyday clinics did not finish the course (Öst et al., Cognitive Behaviour Therapy, 2025)
This page brings together 16 figures from 9 sources, data years 2015–2025 · guidance to 2026, mostly from US, European and multi-country research. How CBT-I works, step by step, is in our CBT-I for insomnia guide.
These figures describe groups of people, not you personally. They’re for information, not medical advice.
How effective is CBT-I for insomnia, night to night?
CBT-I for insomnia improves most of the night-to-night sleep measures. A 2015 review of 20 trials with 1,162 adults found the biggest gains in time awake during the night and in sleep efficiency. Those are exactly what its two main tools target. Total sleep time barely changed by the end of treatment.
19.03 minutes faster to fall asleep, on average, for people who had CBT-I compared with people in control groups.
26.00 minutes less time awake during the night, on average, compared with control groups.
9.91 points higher sleep efficiency (about 10 points), the share of time in bed that is spent asleep.
7.61 minutes more total sleep on average, a change too small to be sure it was real.
What this means for you: In the average trial, the CBT-I group fell asleep faster and woke less in the night than the control group. Total sleep barely moved at first. That fits how CBT-I works: it makes sleep more solid before it makes it longer. Why that happens is explained in the sleep restriction part of our guide.
What is the success rate of CBT-I for insomnia, and how long do the gains last?
About half of people who have CBT-I in everyday clinics are in remission when treatment ends, and slightly more a year later. In trials that compared CBT-I with sleep medicine, about 4 in 10 people who started with CBT-I were in remission at long-term follow-up. Other studies show gains lasting 2 and even 10 years.
41% vs 28% of people were in remission at long-term follow-up when they started with CBT-I, compared with when they started with sleep medicine.
45% and 51% of people in everyday clinics were in remission at the end of CBT-I and about a year later.
48–74% were in remission one year after treatment in one trial, and 44–63% after two years, depending on the treatment order.
66% of people were in remission ten years after a six-week, book-based CBT-I program.
What this means for you: In these studies, “remission” usually means no longer meeting the criteria for insomnia disorder. That is a high bar, not a small improvement. The figures differ because the people, programs and follow-up times differ. What they share is that gains tend to last after treatment ends. If your sleep slips later, the CBT-I questions and answers explain what people usually do next.
How does CBT-I compare with sleep medication — what do the numbers say?
Starting with CBT-I led to more long-term remission than starting with sleep medicine in a 2024 review of trials. People who started with CBT-I were also less likely to drop out. Adding medicine to CBT-I did not clearly beat CBT-I alone at long-term follow-up. These are group averages, not a promise for one person.
21% vs 39% of people dropped out by long-term follow-up when they started with CBT-I, compared with when they started with sleep medicine.
What this means for you: Over the long run, people who started with CBT-I tended to stay with it. Choosing between CBT-I and medicine is still a decision to make with a clinician who knows your health. The CBT-I Compass helps you find a safe first step in about a minute.
How effective is digital CBT-I for insomnia?
Digital CBT-I, delivered by app or online program, had a large effect on sleep in a 2023 review of trials. It also eased symptoms of depression a little. These results come only from digital programs. They are a separate set of studies from the in-person figures above, so the two can’t be compared number for number.
Large effect on sleep from app and online CBT-I programs, compared with control groups.
Small-to-moderate effect on depression symptoms from the same digital programs.
What this means for you: If you can’t see a therapist, a digital program is a real option with good evidence behind it. The guide compares in-person, video, guided online and app formats so you can pick one that fits your life.
CBT-I for insomnia with comorbid obstructive sleep apnea — what does one RCT show?
Adding CBT-I to sleep apnea treatment helped insomnia more than the apnea treatment alone in one trial. The 2020 study followed 121 adults who had both obstructive sleep apnea and insomnia. Everyone used a breathing machine at night (PAP). Because this is a single trial, treat the result as promising rather than settled.
121 adults with both conditions had fewer insomnia symptoms when CBT-I was added to PAP than with PAP alone.
What this means for you: If you snore loudly or stop breathing in your sleep, get checked for sleep apnea first. Treating apnea sometimes eases insomnia on its own. This trial suggests CBT-I can still add benefit on top. The safety questions in our CBT-I answers cover when to ask about a sleep study.
How long does a CBT-I course take — what do different sources report?
A CBT-I course usually takes 4 to 8 sessions over about 6 to 8 weeks, according to Cleveland Clinic. VA/DoD guidance describes 4 to 10 weekly sessions of about an hour. The difference is real, not an error. Courses vary between one-to-one therapy, groups, shorter first steps and digital programs.
4–8 sessions of 30 to 60 minutes each is a typical CBT-I course.
4–10 sessions of about an hour, once a week, is the range in VA/DoD guidance. A shorter version (BBT-I) uses 4.
What this means for you: A short course is often a first step, with more sessions if needed. Progress is tracked with a sleep diary. Our CBT-I diary tool turns your own sleep notes into averages to discuss with your clinician, and it has a blank diary you can print tonight.
What are the safety and dropout numbers for CBT-I?
No harms were reported in the 20 trials of the 2015 review. In everyday clinics, about 14% of people did not finish their course. Neither figure covers everyone. Most trials left out people with conditions that need a tailored plan, such as bipolar disorder or uncontrolled seizures.
No harms were reported across the 20 CBT-I trials in the 2015 review.
13.9% of people who started CBT-I in everyday clinics did not finish it, about 1 in 7.
What this means for you: “No harms reported” does not mean CBT-I is easy for everyone. The AASM guideline notes that sleep restriction can make you sleepier and less focused for a while. Some health conditions need a tailored plan. The CBT-I answers page walks through the safety questions in plain words.
CBT-I for insomnia statistics table
| What it measures | Figure | Who / based on | Compared with · when | Source |
|---|---|---|---|---|
| Sleep onset latency (SOL) improvement | −19.03 min (mean difference) | Adults with chronic insomnia · 20 RCTs · n=1,162 | Inactive controls · posttreatment · 2015 | Trauer et al., Annals of Internal Medicine, 2015 |
| Wake after sleep onset (WASO) improvement | −26.00 min (mean difference) | Adults with chronic insomnia · 20 RCTs · n=1,162 | Inactive controls · posttreatment · 2015 | Trauer et al., Annals of Internal Medicine, 2015 |
| Sleep efficiency (SE%) improvement | +9.91 percentage points (95% CI 8.09–11.73; mean difference) | Adults with chronic insomnia · 20 RCTs · n=1,162 | Inactive controls · posttreatment · 2015 | Trauer et al., Annals of Internal Medicine, 2015 |
| Total sleep time (TST) improvement | +7.61 min (mean difference; CI includes zero — no reliable evidence of change) | Adults with chronic insomnia · 20 RCTs · n=1,162 | Inactive controls · posttreatment · 2015 | Trauer et al., Annals of Internal Medicine, 2015 |
| Long-term remission rate — CBT-I initiation | 41% (95% CI 31–53%); OR 1.82 vs pharmacotherapy (95% CI 1.15–2.87); high certainty | Adults with chronic insomnia · 9 trials · CBT-I arms n=292; pharm arms n=193 | Pharmacotherapy initiation (~28%) · median 24-week follow-up · published 2024 | Furukawa et al., Psychiatry and Clinical Neurosciences, 2024 |
| Remission rate — post-treatment and 12-month follow-up (routine care) | 45% post-treatment; 51% at ~12-month follow-up | Adults in routine clinical care · 32 studies · n=5,231 | Within-group (effectiveness) · ~12-month follow-up · published 2025 | Öst et al., Cognitive Behaviour Therapy, 2025 |
| Remission rate — 12- and 24-month follow-up (RCT) | 48–74% at 12 months; 44–63% at 24 months | Adults with chronic insomnia · n=160 · four CBT-I sequences | Pre-treatment baseline · 12- and 24-month follow-up · published 2017 | Morin et al., Sleep, 2017 |
| Remission rate — 10-year follow-up | 66% | Adults with insomnia disorder · n=133 · bibliotherapy CBT-I (6 weeks) | Pre-treatment diagnosis · 10-year follow-up · published 2022 | Jernelöv et al., Cognitive Behaviour Therapy, 2022 |
| Long-term dropout — CBT-I vs pharmacotherapy | 21% vs 39% (estimated); OR 0.42 (95% CI 0.26–0.66) | Adults with chronic insomnia · trial count for this outcome not reported | Pharmacotherapy initiation · long-term follow-up · published 2024 | Furukawa et al., Psychiatry and Clinical Neurosciences, 2024 |
| Digital CBT-I effect on sleep outcomes | SMD −0.76 (large effect) | Adults using digital CBT-I · 22 trials | Control condition · posttreatment · published 2023 | Lee et al., npj Digital Medicine, 2023 |
| Digital CBT-I effect on depressive symptoms | SMD −0.42 (small-to-moderate effect) | Adults using digital CBT-I · 21 trials | Control condition · posttreatment · published 2023 | Lee et al., npj Digital Medicine, 2023 |
| CBT-I plus PAP vs PAP alone — comorbid OSA and insomnia | Fewer insomnia symptoms with CBT-I + PAP than with PAP alone (observed group comparison; single RCT) | Adults with comorbid OSA and insomnia · n=121 | PAP therapy alone · posttreatment · published 2020 | Ong et al., Sleep, 2020 |
| Typical CBT-I session count — clinic guidance | 4–8 sessions, 30–60 minutes each | General adult population · source-level program description · no study n | No fixed universal comparator · typical program · 2026 | Cleveland Clinic, 2026 |
| Typical CBT-I session count — VA/DoD clinical guidance | 4–10 hour-long weekly sessions | Adults in VA/DoD clinical settings · source-level description · no study n | BBT-I (4 sessions) · typical program · 2025 | VA/DoD Patient Guide, 2025 |
| Adverse outcomes — CBT-I randomized trials | None reported across 20 RCTs | Adults with chronic insomnia · 20 RCTs · n=1,162 | Inactive controls · posttreatment · 2015 | Trauer et al., Annals of Internal Medicine, 2015 |
| Attrition rate — routine clinical care | 13.9% (95% CI 11.1–17.2%) | Adults in routine clinical care · 31 of 32 studies · n=5,231 | Program completion · across program duration · published 2025 | Öst et al., Cognitive Behaviour Therapy, 2025 |
Why the numbers differ
Remission ranges from 41% to 66%. The 41% comes from a 2024 review that compared starting with CBT-I against starting with medicine, at about 24 weeks. It is an estimate. The authors applied the odds ratio (1.82) to the 28% remission seen in the medicine groups. The 66% comes from one study that followed people for 10 years. The studies also define remission differently. Use the 41% to compare CBT-I with medicine. Use the 66% to ask whether gains can last for years.
Everyday clinics (45–51%) vs trials (41%). The clinic studies followed people who all had CBT-I, with no control group. Numbers like these tend to look bigger. The trial review compared two groups directly, which is the stricter test. Both are useful, and they don’t contradict each other.
Session counts: 4–8 vs 4–10. Cleveland Clinic and VA/DoD describe different settings: one-to-one therapy, groups and step-by-step programs. A short 4-session version (BBT-I) is sometimes used first. Neither number is wrong.
Digital “large effect” vs minutes saved. The in-person review measured minutes from sleep diaries. The digital review combined different sleep scales into one effect size. They can’t be compared directly, but both show a meaningful benefit.
What the numbers can’t tell you
Every figure here is an average for a group of people in a study. It can’t tell you whether CBT-I will work for you. Many trials left out people with bipolar disorder, uncontrolled seizures, severe daytime sleepiness, active substance use, acute mental health symptoms or ongoing exposure therapy for PTSD. So the figures may not apply to those groups. The session counts from Cleveland Clinic and VA/DoD describe programs, not study results.
The small gain in total sleep time in the 2015 review was not reliable, so claims that CBT-I “adds hours of sleep” are not supported here. Studies define remission in different ways, which makes comparisons rough. We found no reliable figure for how many people with insomnia get or finish CBT-I. The sleep apnea result comes from one trial only.
How we compiled this page: we gathered figures from the published studies and official sources below, recorded each figure’s outcome, population, comparison, timepoint and year exactly as published, and ran no surveys of our own. The original figures belong to their publishers; our compilation and wording may be reused with credit under CC BY 4.0.
Ready to turn these numbers into a plan that fits you?
The statistics describe groups — your path depends on your situation. Use the CBT-I mind map to see how all the pieces connect, or go straight to the CBT-I compass to find your safest starting point. More in our sleep solutions guide.
See how it all connects →Sources
- Trauer JM et al. — Cognitive Behavioral Therapy for Chronic Insomnia: A Systematic Review and Meta-analysis, Annals of Internal Medicine (2015) — Tier 1 systematic review and meta-analysis; used for: SOL, WASO, SE%, TST improvements; no adverse outcomes finding.
- Furukawa Y et al. — Initial treatment choices for long-term remission of chronic insomnia disorder in adults: a systematic review and network meta-analysis, Psychiatry and Clinical Neurosciences (2024) — Tier 1 NMA, high-certainty evidence; used for: 41% vs 28% long-term remission, 21% vs 39% long-term dropout (both estimated from odds ratios).
- Öst L-G et al. — Cognitive behavioral therapy for adult insomnia disorder in routine clinical care: a systematic review and meta-analysis, Cognitive Behaviour Therapy (2025) — Tier 1 effectiveness meta-analysis; used for: 45%/51% remission rates, 13.9% attrition.
- Morin CM et al. — Long-Term Maintenance of Therapeutic Gains Associated With Cognitive-Behavioral Therapy for Insomnia Delivered Alone or Combined With Zolpidem, Sleep (2017) — Tier 1 RCT long-term follow-up; used for: 12- and 24-month remission rates.
- Jernelöv S et al. — Very long-term outcome of cognitive behavioral therapy for insomnia: one- and ten-year follow-up of a randomized controlled trial, Cognitive Behaviour Therapy (2022) — Tier 1 RCT long-term follow-up; used for: 66% remission at 10 years.
- Lee S et al. — Digital cognitive behavioral therapy for insomnia on depression and anxiety: a systematic review and meta-analysis, npj Digital Medicine (2023) — Tier 1 systematic review and meta-analysis; used for: digital CBT-I sleep SMD −0.76, depression SMD −0.42.
- Ong JC et al. — A randomized controlled trial of CBT-I and PAP for obstructive sleep apnea and comorbid insomnia: main outcomes from the MATRICS study, Sleep (2020) — Tier 1 RCT; used for: CBT-I plus PAP vs PAP alone (121 adults).
- Cleveland Clinic — Cognitive Behavioral Therapy for Insomnia (CBT-I) (2026) — Tier 2 major clinic patient education; used for: 4–8 session count (A2-stat).
- VA/DoD — Treating Insomnia with Behavior Change: A Patient’s Guide (2025) — Tier 1 clinical patient guide; used for: 4–10 session count (A3-stat).
Figures checked · 16 figures from 9 sources · Next review
How we made this page: figures gathered and checked from the sources above, written up with AI assistance and edited by Aamir Bashir, Founder & Editor. Read our editorial policy.