How to fall asleep fast statistics: the key numbers
How to fall asleep fast statistics is one of the most searched sleep questions — and the numbers show why. About 1 in 7 US adults struggles to fall asleep most days or every day (CDC, 2024). CBT-I, the recommended structured treatment, cut the time it took adults to fall asleep by about 19 minutes on average compared with no treatment, across 20 randomised trials. Typical sleep-onset time in healthy adults is around 12 minutes by clinical test, rising only slightly with age.
- 15.4% of US adults had trouble falling asleep most days or every day in 2024 (AASM Newsroom citing CDC, 2026)
- 12% of Americans have been diagnosed with chronic insomnia — about 1 in 8 (AASM Sleep Prioritization Survey, 2024)
- ~19 minutes average reduction in time to fall asleep with face-to-face CBT-I vs. no treatment, across 20 randomised trials (Medscape citing Trauer et al., 2015 meta-analysis)
- ~12 minutes average sleep-onset time for healthy adults on the clinical sleep latency test (Boulos et al., meta-analysis)
- 51% of Americans have never discussed their sleep with any health professional (AASM Sleep Prioritization Survey, 2024)
This page holds 18 figures from 12 sources, with data years from 2015 to 2026, mostly from the US, with global and UK figures included. The full explanation of what these numbers mean is in our article on how long falling asleep should take.
These figures describe groups of people, not you personally. They are for information only, not medical advice.
How common is trouble falling asleep?
Difficulty falling asleep is widespread. About 15 in every 100 US adults struggle to fall asleep most days or every day, according to 2024 CDC data cited by the AASM. Chronic insomnia — the formal disorder — affects roughly 10% of people when strict diagnostic criteria are used. Occasional symptoms touch far more: up to 30–35% of adults each year report some difficulty.
15.4% of US adults had trouble falling asleep most days or every day in 2024 — about 1 in 7 adults
12% of Americans reported having been diagnosed with chronic insomnia — about 1 in 8 adults
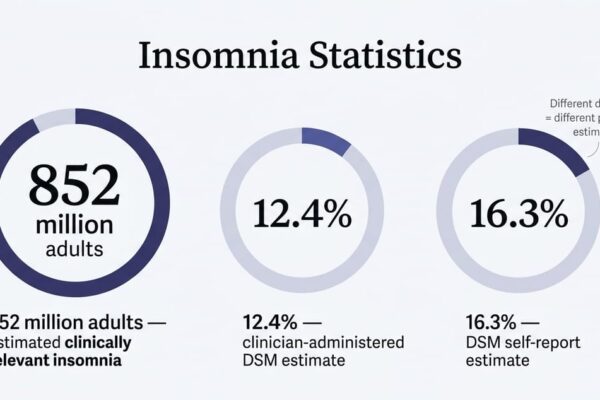
The AASM classification system shows that 10% of the general population has chronic insomnia disorder. This requires meeting strict diagnostic criteria.
30–35% of adults experience passing (transient) insomnia symptoms each year. However, most people do not meet the criteria for the chronic disorder.
A review of 24 worldwide studies found that 13.9% of adults met diagnostic criteria for insomnia disorder. This rate reflects the general population.
What this means for you: Difficulty falling asleep is common enough that you are far from alone — but the figures show that symptoms and full disorders are different things. Our article section on when to get help explains what distinguishes occasional difficulty from something worth discussing with a clinician.
Who is most affected by trouble falling asleep?
Younger adults report the highest rates of nightly difficulty, while older adults show higher rates of insomnia symptoms overall. Women are somewhat more likely to report insomnia than men. Millennials (ages 27–42 in 2024) had the highest rate of diagnosed chronic insomnia of any generation in the US.
A 2024 US survey showed 15% of Millennials reported a chronic insomnia diagnosis. They had the highest rate of any generation surveyed.
18.5% of women and 12.2% of men regularly had trouble falling asleep, based on NHIS data
Healthy adults take 1.1 minutes longer to fall asleep (sleep onset) for each added decade of age. This represents a very small change across a lifetime.
What this means for you: Age makes only a tiny difference to how long falling asleep takes in healthy people. If you are spending much longer awake in bed, the cause is more likely to be stress, habits, or a treatable condition than simply getting older. Our article section on why you are tired but awake covers the common reasons.
How long should it take to fall asleep — the statistics?
On the clinical multiple sleep latency test (MSLT), healthy adults fall asleep in about 12 minutes on average. In everyday bedroom conditions, a range of 10–20 minutes is widely cited. Sleep onset time rises by only about 1 minute per decade of adult life on formal sleep-study measurements. Any of these figures is a group average — not a target you must hit each night.
A review of 110 groups (cohorts) found healthy adults take an average of ~11.7 minutes to fall asleep. Doctors measured this using the clinical multiple sleep latency test.
The Cleveland Clinic describes 10–20 minutes as a typical range for healthy sleepers. This applies to people without sleep problems resting in their own beds.
What this means for you: The 12-minute figure comes from a daytime clinical test — not a bedroom setting. In your own bed, some variation is completely normal. Worrying about hitting a number can itself delay sleep. Our statistics on normal sleep timing sit alongside the Answers page, which tackles common questions about whether five-minute or ten-second sleep claims hold up.
How well does CBT-I work at reducing the time it takes to fall asleep?
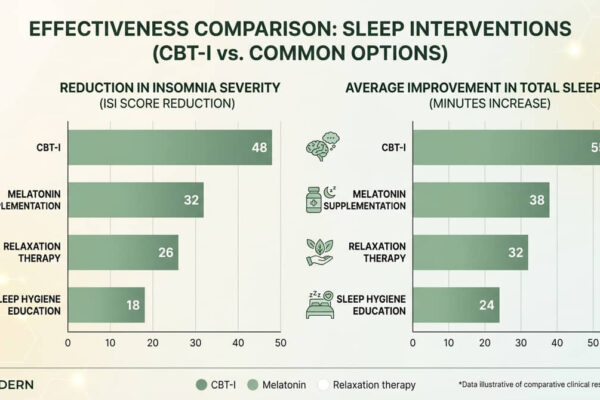
CBT-I (therapy for ongoing insomnia) is the most researched non-drug treatment for difficulty falling asleep. Across multiple meta-analyses, adults with chronic insomnia fell asleep roughly 19 minutes faster after face-to-face CBT-I compared with no treatment. These gains persisted at follow-up checks 3 to 12 months later. A 2015 meta-analysis of 20 trials is the most-cited single source for the 19-minute figure.
A review of 20 randomised trials studied adults with chronic insomnia. Patients fell asleep ~19 minutes faster after CBT-I compared with no treatment.
A review of 37 studies looked at recovery (remission) from insomnia after treatment. It showed 36% of CBT-I patients recovered, compared with 16.9% in control groups.
CBT-I reduced the time it takes to fall asleep (sleep-onset latency) compared to non-active controls. This effect held steady at a 3-month check (Hedges g = 0.38). The improvement remained at 12 months (g = 0.40).
A review of 21 randomised controlled trials showed CBT-I helps working adults fall asleep faster. It improved their sleep-onset latency with an effect size of Hedges g = −0.62.
What this means for you: Spending 19 fewer minutes awake in bed is a meaningful change. It is roughly the difference between waiting half an hour and settling in 10 minutes. The effect size figures show a moderate, large, and lasting benefit. CBT-I is not a one-night fix. However, its evidence is stronger than any technique tried in a single evening. Read more about what CBT-I involves in our treatment options section.
Does online (digital) CBT-I work as well as in-person therapy?
Digital CBT-I delivers the same core components through apps or websites. A 2025 meta-analysis of 14 randomised trials found that digital CBT-I was comparable to therapist-delivered CBT-I, and cut sleep-onset time by about 15 minutes compared with inactive controls. Remote CBT-I showed a similar benefit in an earlier meta-analysis.
A review of 14 randomised trials looked at adults with insomnia. Patients using digital CBT-I saw a 15.53 minutes reduction in time to fall asleep compared to inactive controls.
A review of randomised trials found remote CBT-I produced an 11.78 minutes shorter sleep-onset time versus control conditions. The average difference was MD −11.78 (95% CI −15.74 to −7.82).
What this means for you: Online and app-based CBT-I produces similar results to in-person sessions. If face-to-face access is limited where you live, a digital program is a well-supported option. Our treatment options section lists access routes in the US, UK, Canada and Australia.
Who gets help — and who doesn’t?
Despite effective treatments being available, most people with sleep trouble never discuss it with a health professional. In a 2024 US survey of 2,006 adults, more than half had never raised sleep with any clinician. Only 13% had seen a sleep specialist.
51% of Americans have never discussed their sleep with any health professional, despite sleep problems being common
Only 13% of US adults have discussed their sleep with a sleep specialist. Another 28% have spoken with a primary care professional about it.
What this means for you: If sleep tips have not helped after weeks of trying, you are in good company — and there are clinically supported next steps. Our Compass tool can help you figure out which step fits your situation right now.
Awareness and worry about sleep
Sleep worry itself is nearly universal. In the same 2024 AASM survey, 81% of people said they had lost sleep due to worries about their sleep problems. Younger adults carried the most sleep-related worry — 57% of 18–24-year-olds reported often or always losing sleep over sleep concerns.
81% of US adults reported having lost sleep due to worries about their sleep problems
Surveys show 42% of US adults often or always lost sleep from worrying about sleep problems. This figure rises to 57% among 18–24-year-olds.
What this means for you: Worry about sleep is part of what keeps many people awake — and it is normal, not a sign something is seriously wrong. Our Mind Map shows how worry, habits and environment connect, so you can see the full picture.
How to fall asleep fast statistics table
| What it measures | Figure | Who / based on | Compared with · when | Source |
|---|---|---|---|---|
| Trouble falling asleep most days or every day (US adults, 2024) | 15.4% | US adults · national survey | Sex breakdown: women 18.5%, men 12.2% · 2024 data | AASM Newsroom citing CDC, 2026 |
| Diagnosed with chronic insomnia (US adults, self-report) | 12% | 2,006 US adults · May 2024 survey | Millennials 15%, Baby Boomers 8% · 2024 | AASM Sleep Prioritization Survey, 2024 |
| Chronic insomnia disorder (strict diagnostic criteria) | ~10% of population | General adult population | Short-term insomnia (under 3 months): 15–20% · 2023 | AASM citing ICSD-3-TR, 2023 |
| Transient insomnia symptoms per year | 30–35% | General adult population | Does not meet chronic criteria · annual prevalence · 2023 | AASM citing ICSD-3-TR, 2023 |
| Insomnia disorder prevalence (global meta-analysis, diagnostic tools) | 13.9% (95% CI 10.9–17.6%) | General adult population · 24 studies | Self-report diagnostic tools: 16.3% · published 2025 | van Straten et al., Journal of Sleep Research, 2025 |
| Highest chronic insomnia diagnosis rate by generation (US) | 15% — Millennials | 637 Millennial respondents within 2,006-adult sample | Baby Boomers 8% · Gen Z 14% · May 2024 | AASM Sleep Prioritization Survey, 2024 |
| Sex difference in regular trouble falling asleep (US) | Women 18.5% · men 12.2% | US adults · national survey | Overall 15.4% · 2024 data | AASM Newsroom citing CDC, 2026 |
| Change in sleep-onset time per decade of age (healthy adults, polysomnography) | +1.1 min per decade (95% CI 0.3–1.9) | Healthy adults · 169 PSG studies, 5,273 participants | Baseline across all ages · published 2019 | Boulos et al., Lancet Respiratory Medicine, 2019 |
| Average sleep-onset time in healthy adults (MSLT clinical test) | ~11.7 min (95% CI 10.8–12.6) | Healthy adults · 110 cohorts, 4,058 participants | Earlier vs. later sleep-onset definition: 11.7 vs. 11.8 min · published 2020 | Boulos et al., meta-analysis |
| Typical sleep-onset range in people without sleep problems (bedroom) | 10–20 minutes | Adults without sleep disorders | General clinical estimate · 2025 | Cleveland Clinic, 2025 |
| Reduction in time to fall asleep with CBT-I vs. no treatment (face-to-face, adults) | ~19 minutes (mean difference) | Adults with chronic insomnia · 20 RCTs | No treatment or wait-list control · post-treatment · 2015 | Trauer et al., 2015 meta-analysis |
| Remission from insomnia disorder after CBT-I vs. control (37 studies) | 36% vs. 16.9% | Adults with insomnia · 37 studies | Control conditions · post-treatment · 2015 | Wu et al., 2015, cited in ClinicalTrials protocol |
| Long-term effect of CBT-I on sleep-onset latency at 3 months and 12 months | Hedges g = 0.38 (3m) · 0.40 (12m) | Adults with insomnia · 30 RCTs vs. non-active controls | Non-active controls · 3 and 12 months post-treatment · 2023 | van Straten et al., long-term CBT-I meta-analysis, 2023 |
| CBT-I effect on sleep-onset latency in working adults | Hedges g = −0.62 | Working adults with insomnia · 21 RCTs | Control group · post-treatment · 2023 | Soh et al., PubMed, 2023 |
| Reduction in sleep-onset time with digital CBT-I vs. inactive controls | 15.53 minutes (mean difference) | Adults with insomnia · 14 RCTs · sleep diary data | Inactive controls · post-treatment · 2025 | Benz et al., PMC, 2025 |
| Reduction in sleep-onset time with remote CBT-I vs. controls | 11.78 minutes (MD −11.78, 95% CI −15.74 to −7.82) | Adults with insomnia symptoms · RCTs | Control conditions · post-treatment · 2024 | Hasan et al., Cognitive Therapy and Research, 2024 |
| US adults who have never discussed sleep with a health professional | 51% | 2,006 US adults · May 2024 survey | Discussed with a sleep specialist: 13% · 2024 | AASM Sleep Prioritization Survey, 2024 |
| US adults who have lost sleep due to worries about their sleep | 81% (often or always: 42%) | 2,006 US adults; 18–24 subgroup: 57% often/always · May 2024 | No comparator · 2024 | AASM Sleep Prioritization Survey, 2024 |
Why the numbers differ
The prevalence figures range widely — from about 10% to over 30% — because researchers use different definitions. The 10% figure (AASM, ICSD-3-TR) applies only when symptoms occur three or more nights a week for three months or longer and cause meaningful daytime impairment. The 13.9% figure (van Straten et al., 2025) uses standardised diagnostic tools across 24 studies. The 30–35% figure captures anyone who reports any insomnia symptom in the past year, whether or not they meet the full diagnostic threshold. All three figures are correct — they answer different questions.
The CBT-I sleep-onset improvement figures also vary. The widely cited 19-minute mean difference (Trauer et al., 2015) comes from face-to-face multicomponent CBT-I vs. wait-list or no treatment. Digital CBT-I trials show 11–16 minutes, partly because some used minimal rather than wait-list controls, and partly because digital programs vary in their components. Both figures are from randomised trials of adults with chronic insomnia — not occasional sleepers.
The normal sleep-onset figures differ based on how they are measured. The clinical MSLT takes about 12 minutes under controlled daytime conditions. The 10–20-minute bedroom range reflects everyday self-reporting and clinical estimates. Neither number is wrong. They simply measure different things.
What the numbers can’t tell you
None of the figures on this page predicts your own sleep-onset time tonight. Group averages describe populations, not individuals. The 12-minute MSLT figure comes from healthy adults in a sleep laboratory; your bedroom, stress level and recent sleep history all shift the picture. The CBT-I effect sizes apply to people with chronic insomnia disorder, not to someone who had one bad night.
Relaxation techniques like breathing exercises and progressive muscle relaxation have conditional guideline support for chronic insomnia. However, no reliable published figure exists for their exact timing. We lack data on how many minutes they save against an inactive control group. Because of this, no such figure appears here.
Self-reported figures depend on memory and whether someone actually sought help. These figures cover who has a diagnosis or talked to a doctor. The true rate of undiagnosed chronic insomnia is likely higher than the 12% who report a diagnosis.
We gathered figures for this page from published studies, official health bodies, and national surveys. We recorded each figure’s exact outcome, population, comparison, timepoint, and year. We ran no surveys of our own. The original figures belong to their publishers. You may reuse our compilation and wording with credit under CC BY 4.0.
See how the numbers connect to your situation tonight
The figures here describe groups. The Mind Map links the same research to causes and next steps — worry, tension, room conditions, habits, or ongoing insomnia. More context is in our Sleep Optimization pillar.
See how it all connects →Sources
- AASM — Newsroom: Sleep Facts & Stats (2026) — national health authority statistics page; used for: trouble falling asleep prevalence by sex, chronic insomnia disorder rate, transient insomnia prevalence, short sleep duration
- AASM — Survey shows 12% of Americans have been diagnosed with chronic insomnia (2024) — survey news release; used for: diagnosed chronic insomnia rate
- AASM Sleep Prioritization Survey — Chronic Insomnia (methodology PDF) (2024) — survey methodology; used for: chronic insomnia diagnosis by generation and sex
- AASM Sleep Prioritization Survey — Doctors Talking Sleep (methodology PDF) (2024) — survey methodology; used for: rate of discussing sleep with health professionals
- AASM Sleep Prioritization Survey — Losing Sleep Over Sleep (methodology PDF) (2024) — survey methodology; used for: sleep worry prevalence and frequency
- van Straten et al. — The Prevalence of Insomnia Disorder in the General Population: A Meta-Analysis, Journal of Sleep Research (2025) — peer-reviewed meta-analysis; used for: global insomnia disorder prevalence by diagnostic method
- Boulos et al. — Normal polysomnography parameters in healthy adults: a systematic review and meta-analysis, Lancet Respiratory Medicine (2019) — peer-reviewed meta-analysis; used for: change in sleep-onset latency per decade of age
- Boulos et al. — Normative sleep latency meta-analysis (reported in NeurologyLive) (2020) — meta-analysis of 110 cohorts; used for: average MSLT sleep-onset time in healthy adults
- Cleveland Clinic — How To Fall Asleep Fast (2025) — clinician-reviewed health article; used for: typical bedroom sleep-onset range
- Medscape — CBT Effective for Chronic Insomnia (citing Trauer et al., 2015) (2015 study) — reporting of peer-reviewed meta-analysis findings; used for: 19-minute mean reduction in sleep-onset latency with CBT-I
- Wu et al., 2015 — cited in ClinicalTrials.gov protocol NCT03461666 (2015 meta-analysis, cited 2018) — peer-reviewed meta-analysis cited in clinical protocol; used for: remission rate with CBT-I vs. control
- van Straten et al. — Long-term effects of cognitive behavioral therapy for insomnia: a meta-analysis (Oxford) (2023) — peer-reviewed meta-analysis; used for: long-term effect sizes for sleep-onset latency at 3 and 12 months
- Soh et al. — Effect of CBT-I in workers: A systematic review and meta-analysis, PubMed (2023) — peer-reviewed meta-analysis; used for: CBT-I effect size on sleep-onset latency in working adults
- Benz et al. — Effects of Digital CBT-I on Self-Reported Sleep Parameters: Systematic Review and Meta-Analysis, PMC (2025) — peer-reviewed meta-analysis; used for: digital CBT-I sleep-onset reduction vs. inactive controls
- Hasan et al. — Efficacy of Remote CBT-I: A Meta-analysis, Cognitive Therapy and Research (2024) — peer-reviewed meta-analysis; used for: remote CBT-I sleep-onset latency reduction
Figures checked · 18 figures from 15 sources · Next review
How we made this page: figures gathered and checked from the sources above, written up with AI assistance and edited by Aamir Bashir, Founder & Editor. Read our editorial policy.