Wake up at 3am with anxiety statistics: the key numbers
Wake up at 3am with anxiety statistics cover insomnia, nighttime panic and treatment, because no study we found measured waking at exactly 3am with anxiety. In general-population studies, 13.9% had insomnia disorder. After CBT-I, 36.0% of adults with another condition were in remission, versus 16.9% in comparison groups.
- 13.9% of people in general-population studies had insomnia disorder, pooled across diagnostic methods. (van Straten et al., Journal of Sleep Research, 2025 (DOI: 10.1111/jsr.70089))
- 3 or more times a week for more than 3 months is the guideline bar for chronic insomnia disorder. (VA/DOD, Clinical Practice Guideline, 2025)
- 36.0% of adults with insomnia and another condition were in remission right after CBT-I. (Wu et al., JAMA Internal Medicine, 2015 (DOI: 10.1001/jamainternmed.2015.3006))
- 44–71% of people with panic disorder reported a panic attack that woke them from sleep. (Craske and Tsao, Sleep Medicine Reviews, 2005 (DOI: 10.1016/j.smrv.2004.11.003))
- 6 to 8 weeks is how long a typical CBT-I plan runs. (NHLBI, Insomnia Treatment, 2022)
15 figures from 8 sources, data years 2005–2025, mostly pooled international studies and US, UK and Canadian guidance. The full explanation is in our article on waking at 3am with anxiety.
These figures describe groups of people, not you personally. They’re for information, not medical advice.
How common is waking at 3am with anxiety?
A 2025 meta-analysis pooled a 13.9% rate of insomnia disorder in general-population studies. No study we found measured waking at exactly 3am with anxiety. That is the closest figure we could verify. So 13.9% describes insomnia in general, not that one hour.
13.9% of people in general-population studies met the criteria for insomnia disorder, about 1 in 7, with methods pooled.
What this means for you: Insomnia shows up often in these studies, so you are far from alone. The figure counts insomnia of every kind, so it can’t say how common 3am anxiety is. Our article explains when nighttime waking becomes insomnia.
How often must waking happen before it is chronic insomnia?
At least three times a week for more than three months is the bar the 2025 VA/DoD guideline sets for insomnia disorder. Daytime effects and other causes are also checked before anyone makes the diagnosis. One bad night does not meet that bar.
3 or more times a week for more than 3 months is the pattern the 2025 guideline uses for chronic insomnia disorder.
What this means for you: A few rough nights don’t reach this bar, but you don’t have to wait for it. If sleep trouble makes daily life hard to cope with, book a visit. A diary shows how your own nights compare, and you can fill in or print a night-by-night sleep diary.
How much sleep do adults need?
The NHS gives 7 to 9 hours of sleep a night as the range adults need. Individual needs vary around that range. The figure is about total sleep, not about when you wake. It is guidance for adults in general, not a target you must hit every night.
7 to 9 hours of sleep a night is the range the NHS gives for adults.
What this means for you: Checking the clock to count hours can make wakeful nights harder. Treat 7 to 9 hours as a rough guide, then look at how your days feel. Our article lists what you can change tomorrow to support better sleep.
Why do insomnia prevalence estimates differ?
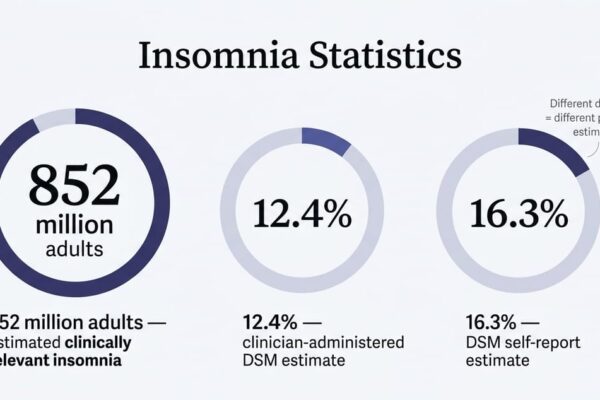
Studies in the 2025 meta-analysis measured insomnia disorder in two ways, and the results differ. Clinician or interviewer diagnoses gave 12.4%. Self-report questions based on the DSM checklist gave 16.3%. Both come from general-population studies.
12.4% of people in general-population studies had insomnia disorder when a clinician or interviewer made the diagnosis, about 1 in 8.
16.3% of people in general-population studies had insomnia disorder when they answered self-report questions based on DSM criteria, about 1 in 6.
What this means for you: Both figures describe insomnia in general, not waking at 3am. A clinician’s diagnosis and a self-report checklist ask different questions, so they give different answers. The Answers page covers how waking anxious differs from having insomnia in short, direct replies.
Does insomnia differ by region?
Pooled insomnia rates in the 2025 meta-analysis ran from 9.9% in Europe to 16.2% in North America and 19.2% in Oceania. Each group used DSM-based definitions. The groups combine different studies, so they are not country figures. Treat the gaps as a caution, not a ranking.
9.9% of people in European studies had insomnia under DSM-based definitions, the lowest of the three regional groups.
16.2% of people in North American studies had insomnia under DSM-based definitions.
19.2% of people in Oceania studies had insomnia under DSM-based definitions, with a very wide range of uncertainty.
What this means for you: Gaps between regions can come from which studies were included and how insomnia was defined. They are not national rankings, and they say nothing about your own nights. Care routes differ by country, and our article lists how to find help and prepare for an appointment.
How common is nighttime panic in people with panic disorder?
In a 2005 clinical review, 44% to 71% of people with panic disorder reported at least one panic attack that woke them from sleep. That group already had a panic disorder diagnosis. The figure does not apply to everyone who wakes anxious at 3am.
44–71% of people already diagnosed with panic disorder reported at least one panic attack that woke them from sleep.
What this means for you: Waking anxious does not mean you have panic disorder. These people already had that diagnosis, so the range can’t be applied to everyone who wakes at 3am. If sudden, intense symptoms wake you, our article compares nighttime panic with anxious thinking.
How often does CBT-I lead to insomnia remission?
In all, 539 people had CBT-I and 482 were in comparison groups. CBT-I had 3.28 times the odds of remission. Odds are not the same as individual chances. Trials counted remission in their own ways.
36.0% of adults with insomnia and another psychiatric or medical condition were in remission right after CBT-I.
16.9% of similar adults in control or comparison groups were in remission at the same point.
3.28 times the odds of insomnia remission after CBT-I, compared with control groups, in adults with another health condition.
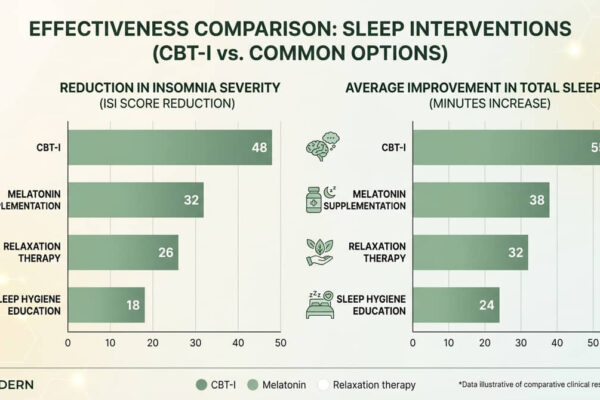
What this means for you: Group results show the gap between treatment and comparison, not what will happen to one person. Odds compare groups and are not your chance of success. Our article sets out how CBT-I compares with basic sleep tips and medicine.
How long does CBT-I take?
A 6- to 8-week plan is how NHLBI describes CBT-I, while CAMH’s clinical guidance says it usually takes three to six sessions. These measure different things and don’t necessarily clash. Programs vary, so your clinician sets the pace.
6 to 8 weeks is how long a typical CBT-I treatment plan runs.
3 to 6 sessions is how many sessions CBT-I usually takes in CAMH’s clinical guidance.
What this means for you: Weeks and sessions are two ways to describe a short course. CBT-I can run in person, by phone or online. When you are ready to choose a step, the Compass routes you by what you are facing.
How long should you keep a sleep diary?
One to two weeks is how long NHLBI suggests keeping a sleep diary before you see a doctor about insomnia. A diary records when you sleep, wake and nap each day. It helps a clinician see your pattern. It does not diagnose anything.
1 to 2 weeks is how long NHLBI suggests keeping a sleep diary before seeing a doctor about insomnia.
What this means for you: One to two weeks of short morning notes gives a clinician something concrete to read. You can start tonight with a few words each morning. Our article shows how to keep track of your nights without watching the clock.
Wake up at 3am with anxiety statistics table
| What it measures | Figure | Who / based on | Compared with · when | Source |
|---|---|---|---|---|
| Insomnia disorder, both diagnostic methods pooled | 13.9% · pooled prevalence, 95% CI 10.9%–17.6% | General-population samples · 24 prevalence estimates | No comparison · cross-sectional · published 2025 | van Straten et al., Journal of Sleep Research, 2025 (DOI: 10.1111/jsr.70089) |
| Pattern for chronic insomnia disorder | 3 or more times a week · diagnostic threshold | Adults with insomnia symptoms · not applicable | More than 3 months · 2025 | VA/DOD, Clinical Practice Guideline, 2025 |
| Sleep adults need | 7 to 9 hours · recommended range | Adults · not applicable | Per night · 2024 | NHS, Insomnia, 2024 |
| Insomnia disorder by clinician or interviewer diagnosis | 12.4% · pooled prevalence, 95% CI 9.0%–16.8% | General-population samples · 14 prevalence estimates | Self-report DSM method · cross-sectional · published 2025 | van Straten et al., Journal of Sleep Research, 2025 (DOI: 10.1111/jsr.70089) |
| Insomnia disorder by self-report DSM questions | 16.3% · pooled prevalence, 95% CI 11.3%–23.0% | General-population samples · 10 prevalence estimates | Clinician or interviewer diagnosis · cross-sectional · published 2025 | van Straten et al., Journal of Sleep Research, 2025 (DOI: 10.1111/jsr.70089) |
| Insomnia in European study groups | 9.9% · subgroup pooled estimate, 95% CI 6.4%–20.2% | General-population samples · 10 studies | North American and Oceania groups · cross-sectional · 2025 | van Straten et al., Journal of Sleep Research, 2025 (DOI: 10.1111/jsr.70089) |
| Insomnia in North American study groups | 16.2% · subgroup pooled estimate, 95% CI 11.4%–22.6% | General-population samples · 5 studies | European and Oceania groups · cross-sectional · 2025 | van Straten et al., Journal of Sleep Research, 2025 (DOI: 10.1111/jsr.70089) |
| Insomnia in Oceania study groups | 19.2% · subgroup pooled estimate, 95% CI 2.8%–27.8% | General-population samples · 4 studies | European and North American groups · cross-sectional · 2025 | van Straten et al., Journal of Sleep Research, 2025 (DOI: 10.1111/jsr.70089) |
| Panic attacks that wake people from sleep | 44–71% · reported range | People with panic disorder · number not reported in the abstract | No comparison · ever occurring · 2005 | Craske and Tsao, Sleep Medicine Reviews, 2005 (DOI: 10.1016/j.smrv.2004.11.003) |
| Remission after CBT-I | 36.0% · observed pooled proportion | Adults with insomnia and another condition · 539 patients, 22 trials | Control or comparison groups · post-treatment · 2015 | Wu et al., JAMA Internal Medicine, 2015 (DOI: 10.1001/jamainternmed.2015.3006) |
| Remission in control or comparison groups | 16.9% · observed pooled proportion | Adults with insomnia and another condition · 482 patients, 22 trials | CBT-I groups · post-treatment · 2015 | Wu et al., JAMA Internal Medicine, 2015 (DOI: 10.1001/jamainternmed.2015.3006) |
| Odds of remission, CBT-I versus controls | 3.28 · pooled odds ratio, 95% CI 2.30–4.68 | Adults with insomnia and another condition · 1,021 participants, 22 trials | Control or comparison groups · post-treatment · 2015 | Wu et al., JAMA Internal Medicine, 2015 (DOI: 10.1001/jamainternmed.2015.3006) |
| Typical CBT-I plan length in weeks | 6 to 8 weeks · descriptive | People receiving CBT-I · number not reported | No comparison · treatment course · 2022 | NHLBI, Insomnia Treatment, 2022 |
| Typical CBT-I plan length in sessions | 3 to 6 sessions · descriptive | Insomnia patients in CAMH guidance · number not reported | No comparison · treatment course · 2019 | CAMH, Sleep Disorders: Treatment, 2019 |
| Sleep diary length before a visit | 1 to 2 weeks · preparation guidance | People preparing to see a doctor about insomnia · not applicable | No comparison · before the visit · 2022 | NHLBI, Insomnia Diagnosis, 2022 |
Why the numbers differ
General-population insomnia shows three figures: 12.4%, 13.9% and 16.3%. The first rests on clinician or interviewer diagnoses and the last on self-report questions. The middle figure pools both methods. Use 12.4% when you want diagnosed insomnia, and 16.3% when you want people whose answers match the checklist.
Regional figures of 9.9%, 16.2% and 19.2% come from groups of 10, 5 and 4 studies. Different studies and definitions sit behind each one, and the Oceania range is very wide. Read them as study groups, not national rates.
CBT-I length is given as 6 to 8 weeks by one source and three to six sessions by another. One counts time and the other counts visits, so they don’t clash.
The 44% to 71% panic range and the 13.9% insomnia rate answer different questions. One covers people already diagnosed with panic disorder and the other covers general-population samples. Comparing them would mislead.
Remission of 36.0% versus 16.9% and the 3.28 times the odds describe the same trials in two ways. The percentages show the groups side by side, and the odds sum up the gap.
What the numbers can’t tell you
No reliable figure shows how often people wake at exactly 3am with anxiety. We also did not verify a reliable figure for how this pattern affects daily life, how it changes over time, how many people stop treatment, or how many people know about it. These wake up at 3am with anxiety statistics show what research measured, and nothing beyond that.
Definitions change numbers. Interview diagnosis and self-report give different insomnia rates, and the CBT-I trials covered only adults with another medical or psychiatric condition. The panic range comes from people already diagnosed, and we could check it only in the review’s abstract, so its time frame is unknown.
Every figure describes groups, not individuals, and none shows cause and effect. A number can’t tell you why you wake, what you have or what will work for you. A clinician can.
How we compiled this page: we gathered figures from the published studies and official sources below, recorded each figure’s outcome, population, comparison, timepoint and year exactly as published, and ran no surveys of our own. The original figures belong to their publishers; our compilation and wording may be reused with credit under CC BY 4.0.
Turn the numbers into your next step
Numbers describe groups. The Mind Map shows how possible causes, patterns and next steps connect. More in mental health and sleep.
See how it all connects →Sources
- Department of Veterans Affairs and Department of Defense — VA/DOD Clinical Practice Guideline for the Management of Chronic Insomnia Disorder and Obstructive Sleep Apnea (2025) — final clinical guideline; used for: how often and how long sleep trouble must last to count as chronic insomnia.
- Journal of Sleep Research — The Prevalence of Insomnia Disorder in the General Population: A Meta-Analysis (2025) — systematic review and meta-analysis; used for: how common insomnia is overall, by diagnosis method and by region.
- JAMA Internal Medicine — Cognitive Behavioral Therapy for Insomnia Comorbid With Psychiatric and Medical Conditions: A Meta-analysis (2015) — systematic review and meta-analysis of randomized trials; used for: remission after CBT-I compared with control groups.
- National Heart, Lung, and Blood Institute — Insomnia Treatment (2022) — official health guidance; used for: how many weeks a CBT-I plan lasts.
- National Heart, Lung, and Blood Institute — Insomnia Diagnosis (2022) — official health guidance; used for: how long to keep a sleep diary before a visit.
- NHS — Insomnia (2024) — national health-service advice; used for: hours of sleep adults need.
- Centre for Addiction and Mental Health — Sleep Disorders: Treatment (2019) — clinical education; used for: how many sessions CBT-I usually takes.
- Sleep Medicine Reviews — Assessment and treatment of nocturnal panic attacks (2005) — narrative clinical review; used for: nighttime panic in people with panic disorder.
Figures checked · 15 figures from 8 sources · Next review
How we made this page: figures gathered and checked from the sources above, written up with AI assistance and edited by Aamir Bashir, Founder & Editor. Read our editorial policy.