

Insomnia is trouble falling asleep, staying asleep, or waking too early, even when you have time and a good chance to sleep, along with daytime effects like tiredness. For chronic insomnia, guidelines recommend cognitive behavioral therapy for insomnia, or CBT-I, as the starting treatment, and most people begin sleeping better within a few weeks.
Based on the 2021 AASM behavioral guideline and the ACP guideline · see what CBT-I includes

If you’re staring at the ceiling at 3am doing sleep math, “how am I going to get through tomorrow?”, you’re not being dramatic. People who share their nights online describe the same loop: tips tried, a flicker of hope, then dread as bedtime comes around again.
This guide is built for that moment. It helps you name your pattern, try safe steps tonight, and decide when CBT-I or a doctor visit makes sense. It’s part of our Sleep Disorders guides.
Not sure which part applies to you? The insomnia Sleep Compass points you to your starting point in about a minute.
Is this you? Find the line closest to your nights.
- “I snap awake at 3am and can’t get back to sleep.” → what to do tonight
- “The tips didn’t help and it’s been months.” → when to see a doctor
- “CBT-I sounds scary. Will I still function?” → how CBT-I works
- “I can’t find a provider or afford weekly visits.” → how to get started
Recognizing yourself here isn’t a diagnosis. It just shows you the best place to start reading.
This guide explains insomnia for general education. It can’t diagnose you or replace care from a clinician who knows your health.
What should you do when you can’t sleep tonight?
When you can’t sleep tonight, the guideline-backed move is to stop lying there fighting it. If you’re awake and frustrated, get out of bed, do something quiet and calm, and go back only when you feel sleepy. This approach is called stimulus control, and it’s used instead of staying in bed to catch up.
Your tonight checklist
- Hold one wake time — Choose a get-up time you can keep every day while you track your sleep. A steady wake time is a core CBT-I step.
- Get up when you’re awake and frustrated — Leave the bed, sit somewhere comfortable, and do something quiet and calm, like reading. Go back when you feel sleepy.
- Plan your up-time before bed — Decide where you’ll sit and what you’ll do, so 3am isn’t a decision you have to make half asleep.
- Start a sleep diary — Jot down how you slept each morning. One to two weeks of entries is the baseline CBT-I providers start from.
For some readers, 3am is the hardest hour. Waking in the night and not drifting back is sometimes called maintenance insomnia (trouble staying asleep), and CBT-I is used to treat it. Our guide to 3am waking patterns and what helps goes deeper.
A printable checklist and diary grid for these steps are in our insomnia sleep diary and stimulus control tool. For short calming skills to use during your up-time, see how to fall asleep fast. If you suspect your room is part of the picture, light, noise and temperature fixes are covered separately.
These steps are a starting point, not treatment. If changing your habits hasn’t helped, or it’s been going on for months, read when to see a doctor. If you feel unable to cope or keep yourself safe, get urgent support rather than waiting for an appointment. Tonight, you can now act on a plan instead of lying there bargaining with the clock.
What is insomnia, and what isn’t it?
Insomnia is trouble falling asleep, staying asleep, or waking earlier than you want, even though you have the time and conditions to sleep, plus daytime effects such as feeling tired or struggling with daily activities. It’s about how your sleep affects your days, not only how many hours you get.
In everyday terms it can look like trouble falling asleep, waking in the night and struggling to drift back off, waking too early, or sleep that doesn’t leave you refreshed. The NHS (2024) guide to insomnia covers the same ground in more depth.
What it isn’t: a single bad night, or proof that something is permanently wrong with you. Other sleep disorders, such as sleep apnea, can also sit behind poor sleep and need different care, which is why a doctor visit matters if something doesn’t fit.
Follow-up worries, such as whether insomnia is dangerous, are covered on our insomnia questions page, and the short version is that the concern centers on how it affects your days and any health conditions alongside it. Next, you can check how your own nights compare.
Is it insomnia disorder or just a rough patch?
Insomnia disorder is usually described as sleep trouble at least three nights a week for at least three months, with daytime effects. Shorter stretches of poor sleep, lasting days to weeks, are called acute insomnia. Only a clinician can say which fits you, but the timeline gives you a useful starting point.
| Pattern | Typical timeline | Sensible next move |
|---|---|---|
| Acute insomnia | Days to weeks | Try the tonight steps above. See a doctor if changing your habits hasn’t helped. |
| Chronic insomnia disorder | At least 3 nights a week for at least 3 months, with daytime effects | CBT-I is the treatment guidelines recommend. Book a review to talk it through. |
This timeline follows the AASM behavioral treatment guideline (2021) and NHS guidance. How long it lasts varies from person to person. What the trials show is that CBT-I improves sleep measures for adults with insomnia.
How many people are in this boat? A 2025 meta-analysis from van Straten and colleagues (2025) pooled studies and estimated that about 12.4% of the general population (95% CI 9.0% to 16.8%) were diagnosed with insomnia disorder in interview-based studies. The estimate varied between studies, so treat it as a rough picture. See every figure with its source.
If your nights fit the longer pattern, you’re reading the right page. The next sections explain why it keeps going and what helps.
At a glance
- CBT-I — Both the AASM and ACP guidelines recommend it for chronic insomnia.
- Sleep hygiene alone — Most people with chronic insomnia need more than basic sleep hygiene tips.
- Typical course — Four to eight sessions of 30 to 60 minutes, weekly or every other week, with improvement often within a few weeks.
- Melatonin and diphenhydramine — The AASM suggests not using either to treat chronic insomnia.
- Progress — A one-to-two-week sleep diary tracks it. In trials, sleep efficiency and time awake at night improved with CBT-I.
Why does insomnia happen? Triggers versus keep-it-going habits
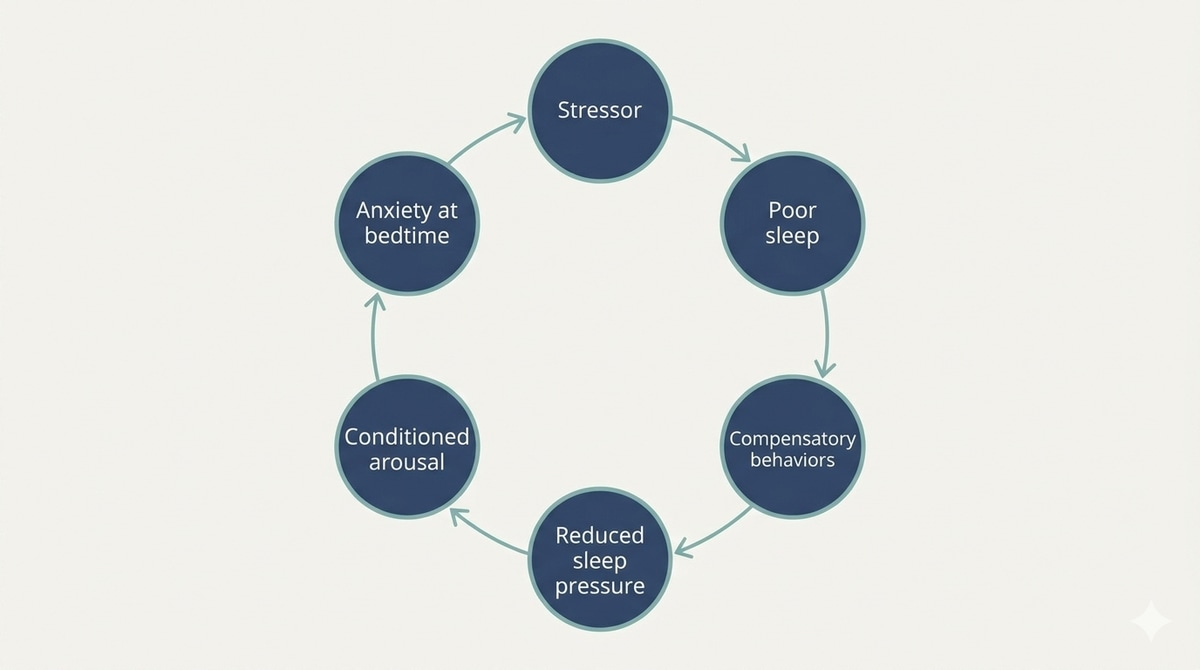
Insomnia usually isn’t caused by one thing. A trigger, such as stress, a schedule change, a substance or a health condition, can start poor sleep, and learned habits can keep it going long after the trigger fades. Seeing both parts makes it easier to choose what to change.
- Stress and a racing mind — Worry can start poor sleep. If your mind races at lights-out, see what helps when your mind races at bedtime.
- Substances — What you drink and when can play a part. Two places to start are caffeine timing and how alcohol relates to sleep.
- Schedule — Irregular days can feed the problem, which is why a steady wake time is part of CBT-I.
- Health conditions — Anxiety, depression or pain can drive insomnia, and CBT-I is still an option, as covered on our insomnia answers page.
- Learned habits — Hours of lying awake and worrying can become a pattern of their own. This is often the part that keeps insomnia going.
The stress loop is its own topic: how stress and sleep feed each other. If it helps to see how the pieces connect, the insomnia mind map lays patterns and next moves side by side.
“Sleep hygiene fixes insomnia.”
Most people with chronic insomnia need more than basic sleep hygiene tips. The AASM advises using them within CBT-I, not on their own.
“Melatonin or antihistamines fix chronic insomnia.”
The AASM suggests not using melatonin or diphenhydramine to treat chronic insomnia.
“If I can’t sleep, I should stay in bed longer to catch up.”
Guidelines point to getting out of bed when you’re awake and returning when sleepy.
You don’t need to find the single cause. Pick the contributor you can change first, then keep reading for the treatment that targets the habits.
What is CBT-I for insomnia, and how does it work?
CBT-I, short for cognitive behavioral therapy for insomnia, is a structured program that changes the habits and thoughts keeping you awake. Guidelines recommend it for chronic insomnia. It typically includes a fixed wake time, leaving bed when awake, limiting time in bed, relaxation, and cognitive skills, and it doesn’t rely on sleeping pills.
CBT-I: the core pieces
CBT-I targets the habits and worries that keep insomnia going. It’s recommended in guidelines from the AASM and the ACP, and trials show average gains in how fast people fall asleep and how long they stay awake at night.
Realistic expectation: most people start sleeping better within a few weeks, but the first weeks can leave you more tired. Limiting time in bed is best set up with a trained provider or program, not on your own.
The American College of Physicians (2016) and the AASM (2021) both recommend CBT-I for insomnia that has become chronic. As an insomnia treatment, it differs from sleep aids because it changes habits and thinking rather than adding a substance. For a fuller walkthrough, see what CBT-I includes.
What changed in trials? A 2015 AHRQ evidence review (2015) pooled self-reported results for adults with insomnia. These are estimated average differences right after treatment, compared with people who got no active treatment:
- Time to fall asleep — 12.7 minutes shorter (15 trials, 1,246 adults).
- Time awake after first falling asleep — 22.3 minutes shorter (11 trials, 832 adults).
- Total sleep time — 14.2 minutes longer (15 trials, 1,233 adults), though this result showed signs of reporting bias.
- Sleep efficiency — 7.2 percentage points higher (15 trials, 1,230 adults).
Those are group averages, so your own results may differ. “CBT-I was brutal” is something real people say, and so is “I didn’t notice any improvement.” Limiting time in bed can mean short-term tiredness, which is why it’s usually adjusted step by step with support from a trained provider or program. If it isn’t helping, the troubleshooting section covers what to try next.
Here’s how it might look for someone who wakes at 3am most nights. They’d spend the first week or two filling in a diary, then work with a provider to set a sleep window based on it and adjust that window as their sleep efficiency changes. The aim isn’t to lie in bed longer, but to spend more of your time in bed asleep. Our CBT-I starter panels and printable diary show how those first two weeks fit together.
Digital CBT-I or a therapist: which fits you?
Both digital and therapist-led CBT-I can help, so the better fit usually comes down to access, cost and how much support you want. CBT-I can be delivered in person, by telehealth, or through an app, and when access is limited, the AASM suggests starting with a digital program.
That’s one named program reviewed in the UK, not an endorsement of any product. You can read the NICE committee discussion (2022) yourself. The AASM also keeps a resource on digital CBT-I platforms and their characteristics (2024), which is a good place to compare options.
A simple way to choose: ask what you can reach soon, what you can afford, and how much support you want. If weekly visits with a therapist aren’t realistic (one reader asked what helps when they couldn’t afford one), a digital program is where the AASM suggests starting. Digital CBT-I for insomnia can be followed by therapist-delivered CBT-I when more support is needed.
Insomnia treatment with medicines: where do they fit?
Sleep medicines have a specific role in insomnia treatment. Guidelines consider them mainly when CBT-I isn’t possible or leaves problems behind, and in NHS care sleeping pills are rarely prescribed, and only for a few days or weeks. Several over-the-counter and supplement options aren’t recommended for chronic insomnia.
| Option | What the guidelines and data show | Limits |
|---|---|---|
| Melatonin, diphenhydramine (an antihistamine), valerian, tryptophan, trazodone | The AASM (2017) suggests not using these to treat chronic insomnia. | This is the guideline’s position for chronic insomnia. Whether any other reason applies is a question for your clinician. |
| Suvorexant (a dual orexin receptor antagonist) | In the guideline’s data, 20 mg lowered time awake after falling asleep by 28.1 minutes versus placebo, measured in a sleep lab (one study, 173 adults). | A single-study estimate. A dose used in a study isn’t advice for you. |
| Other prescription options (such as low-dose doxepin, ramelteon, zolpidem, eszopiclone) | Reviewed in the AASM 2017 pharmacologic guideline. | Whether one makes sense is a decision for you and a clinician. |
| CBT-I plus medication | The AASM (2026) suggests CBT-I plus medication over medication alone, and suggests against choosing the combination over CBT-I alone. | Conditional suggestions, based on low-certainty evidence. |
In plain terms, the AASM combination guideline (2026) suggests that if medicine is used, adding CBT-I is better than medicine alone, and that adding a medicine isn’t a routine step for people doing CBT-I alone. Both are conditional, so treat them as a conversation starter, not a rule.
The numbers in the table come from the AASM pharmacologic guideline (2017). The suvorexant figure is a single-study estimate, so it’s a thin base for big decisions.
Worried you’ll be stuck on pills forever? That worry is understandable, and the NHS notes sleeping pills are prescribed only for a few days or weeks at most. Our insomnia questions page takes the “will I need medicine forever?” question further.
Starting, stopping or changing any medicine belongs in a conversation with a clinician who knows your health. You can now go into that conversation knowing what to ask, including whether CBT-I is possible first.
When should you see a doctor or sleep clinic?
See a doctor if changing your sleep habits hasn’t helped, if you’ve had trouble sleeping for months, or if poor sleep is affecting your daily life. Also ask about a sleep clinic if your nights come with signs of another sleep disorder, such as sleep apnea.
The NHS, Mayo Clinic and MedlinePlus give the same core advice: contact your provider if you’re often tired in the daytime or lack of sleep makes everyday activities hard. That’s the bar, and it’s lower than many people think, so you don’t need a crisis first.
- Breathing and snoring — Do you snore loudly, or does anyone notice pauses in your breathing? Our guide to snoring, pauses and sleep apnea explains why that matters.
- Leg urges — Do you feel urges to move your legs at night? Read about restless legs syndrome, then raise it with your clinician.
- Months of trouble — If tips and habit changes haven’t helped, book a review rather than waiting longer.
Bring one to two weeks of sleep diary entries and a list of what you’ve tried. A diary gives your clinician a clearer picture of your nights.
If you can’t wait for an appointment and feel unable to cope or keep yourself safe, get urgent support now. If you’re in immediate danger, call your local emergency number. You can now tell whether it’s time to book, and what to bring.
How do you get CBT-I or other insomnia treatment?
To get CBT-I, you can see a trained provider in person or by telehealth, or use an app-based program. Providers typically see people for four to eight sessions of 30 to 60 minutes. If access is limited, start with a digital program, and bring your sleep diary to any appointment.
- Start a diary this week. One to two weeks of daily entries gives a provider the baseline they use to set your sleep window.
- Pick a format. CBT-I for insomnia can be effective in person, via telehealth, or even with an app, according to the AASM patient guide (2021).
- If a therapist isn’t within reach or budget, the AASM suggests a digital program first, then therapist-delivered CBT-I.
- Talk to your doctor. They can discuss your options and check for other sleep disorders that need a different route.
Questions worth asking: Will this be in person, by telehealth or by app? How many sessions should I expect? Could another sleep problem be involved? Cost is a real barrier, and no single option fits everyone, so choose the route you can actually keep up with.
Print your 14-day CBT-I starter diaryA diary grid and checklist you can fill in before your first visit.How do you tell it’s getting better? Diary, sleep efficiency and more
Track progress with a daily sleep diary, starting with one to two weeks of baseline entries before treatment begins. Sleep efficiency is the share of your time in bed that you actually spend asleep. In trials, CBT-I improved it, along with time to fall asleep and time awake at night.
- Sleep onset latency — how long it takes you to fall asleep.
- Wake after sleep onset — time spent awake after you first fall asleep.
- Sleep efficiency — time asleep divided by time in bed.
On the Insomnia Severity Index, a questionnaire, scores averaged 5.15 points lower after treatment in a pooled analysis of five trials (345 adults) compared with passive control. For the full set of figures, see our insomnia statistics page.
Did you know?
7.2 percentage points: the average rise in sleep efficiency after CBT-I versus passive control in a 2015 review of 15 trials, alongside 22.3 fewer minutes awake at night. See the figures behind it
One forum reader said they’d recommend CBT-I to anyone with chronic insomnia, while another saw no improvement. Your diary tells you which camp you’re in with numbers instead of dread. Pick one number to watch, and you’ll notice small gains that nights alone can hide.
What if it isn’t working, or the problem comes back?
If CBT-I feels too hard, isn’t helping yet, or insomnia returns after a good stretch, treat it as a problem to troubleshoot, not proof you’re broken. Check your diary, ask your provider to adjust the plan, and see a doctor if nothing shifts, since another sleep problem may be involved.
Setback: the first weeks leave you more tired
Short-term tiredness can come with limiting time in bed, which is one reason some people find CBT-I brutal. Don’t quietly quit. Tell your provider, who can adjust your sleep window step by step, or check whether your app offers coaching or support. Keep filling in your diary so any change is based on your numbers, not on how one bad night felt.
If your diary shows little change after a fair try, it’s reasonable to ask whether another insomnia treatment, or another sleep problem such as sleep apnea or restless legs, is in play. Medicines are one option clinicians weigh when CBT-I leaves problems behind, and the medicines section shows where they fit.
Once sleep improves, ask your provider which habits to keep and how to handle a rough patch if it returns. Your diary gives you a record to compare against, so a bad week doesn’t have to feel like starting over.
Key takeaways
- Remember — Insomnia usually has triggers and habits that keep it going, and basic sleep tips alone rarely resolve it.
- Do — Start a sleep diary and get out of bed when you’re awake and frustrated instead of lying there fighting it.
- If it continues — See a doctor if it has lasted months or affects your days, and get urgent support if you can’t cope or keep yourself safe.
You know your pattern, tonight’s steps and where to start
Not sure whether to begin tonight, try a digital program, or book a visit? The insomnia Sleep Compass helps you pick. More in Sleep Disorders guides.
Find your starting route →Frequently asked questions
Should I stay in bed if I can’t sleep?
No, staying in bed while you’re awake isn’t what the guidelines suggest for insomnia. Under stimulus control, you get up when sleep isn’t coming, keep the activity calm, and return to bed once you feel sleepy. Waiting in bed for sleep to arrive is the habit this approach is designed to replace.
The full steps, including planning where you’ll sit, are in the tonight plan.
How many CBT-I sessions do I need, and how long does it take?
CBT-I typically takes four to eight sessions with a trained provider, each lasting 30 to 60 minutes, usually weekly or every other week. Most people start sleeping better within a few weeks, though your own pace may differ. Your diary will show whether you’re on track.
Does melatonin help chronic insomnia? What about antihistamines?
Melatonin and the antihistamine diphenhydramine aren’t suggested by the AASM for treating chronic insomnia in adults. That’s a statement of the guideline’s position, not a verdict on every use of these products. If you already take either, check with a clinician before changing anything.
How much sleep do adults need?
Many adults do well on about seven to nine hours of sleep, but insomnia is judged by how you function, not only by hours. Sleep that leaves you tired or struggling through the day matters more than hitting an exact number. If sleep is costing you your days, that’s worth raising with a doctor.
Can I nap during CBT-I?
Napping is usually discouraged early in CBT-I, so follow the plan your provider or program gives you. Because your plan is built from your sleep diary, ask before adding naps, and note any you do take so your provider sees the whole picture.
Sources
- American Academy of Sleep Medicine — Combination treatment for chronic insomnia disorder in adults: an AASM clinical practice guideline (2026). Supports: CBT-I plus medication versus either alone (conditional, low certainty).
- American Academy of Sleep Medicine — Behavioral and psychological treatments for chronic insomnia disorder in adults (2021). Supports: definition and timeline, CBT-I components, stimulus control, contributors.
- American College of Physicians — Management of Chronic Insomnia Disorder in Adults (2016). Supports: recommendation of CBT-I for chronic insomnia.
- American Academy of Sleep Medicine — Clinical Practice Guideline for the Pharmacologic Treatment of Chronic Insomnia in Adults (2017). Supports: medicines and supplements not suggested; suvorexant data.
- Agency for Healthcare Research and Quality — Management of Insomnia Disorder, Comparative Effectiveness Review No. 159 (2015). Supports: trial averages for falling asleep, time awake, total sleep time, sleep efficiency and ISI.
- NHS — Insomnia (2024). Supports: definition, when to see a GP, sleeping pills prescribed rarely, sleep clinic referral.
- NIH MedlinePlus — Sleep and your health: When to call the doctor (2026). Supports: when to contact a provider.
- American Academy of Sleep Medicine — Patient Guide: Behavioral & Psychological Treatments for Chronic Insomnia Disorder (2021). Supports: sessions, format options, sleep hygiene limits.
- NICE — Sleepio to treat insomnia and insomnia symptoms (Committee discussion) (2022). Supports: digital CBT-I versus treatment as usual.
- American Academy of Sleep Medicine — Digital CBT-I platforms and characteristics (2024). Supports: digital CBT-I when access is limited.
- van Straten et al., Journal of Sleep Research — The Prevalence of Insomnia Disorder in the General Population: A Meta-Analysis (2025). Supports: pooled prevalence estimate.
- NHS — Every Mind Matters: Sleep problems (2026). Supports: urgent support advice.
- Mayo Clinic — Insomnia: Symptoms and causes (2024). Supports: contributors and when to see a doctor.
- Cleveland Clinic — Cognitive Behavioral Therapy for Insomnia (CBT-I) (2026). Supports: session length and frequency.
- Ong et al. — CBT-I: A Primer (2022). Supports: sleep diary baseline of one to two weeks.
Sources checked · Next review
How we made this guide: researched from the sources above, drafted with AI assistance and edited by Aamir Bashir, Founder & Editor. Read our editorial policy.



