

Natural insomnia treatment includes drug-free therapy, supportive habits, and supplements with different levels of evidence. For persistent insomnia, structured CBT-I is strongly recommended, while good sleep habits alone are insufficient treatment. Some approaches may help sleep feel better without resolving insomnia. Compare their purpose and safety, then find suitable care.
Based on the 2025 VA/DoD guideline and the American Academy of Sleep Medicine guidelines · see every option side by side

You’ve tried the tips, the teas and maybe a few supplements. It still feels like nothing sticks. That’s tiring, and it’s fair to wonder whether medication is the only route left.
This guide sorts the drug-free options by what each one was studied for. You’ll see which have guideline support, which are uncertain, and how to reach care in the US, UK, Canada or Australia. It’s part of our sleep disorders hub.
Not sure which part applies to you? The Natural Insomnia Treatment Sleep Compass points you to your starting point in about a minute.
Is this you? Pick the line that sounds most like your last few months.
- I’ve tried everything and nothing sticks. → why tips alone fall short
- I’ve spent a lot on natural remedies. → what the evidence says about each one
- It sounds like medication is the only route left. → how drug-free care can fit
- It’s still a nightly challenge. → how to review progress and reassess
Seeing yourself in these lines is recognition, not a diagnosis.
This guide explains natural insomnia treatment for general education. It can’t diagnose you or replace care from a clinician who knows your health.
Which natural insomnia treatment options are worth considering?
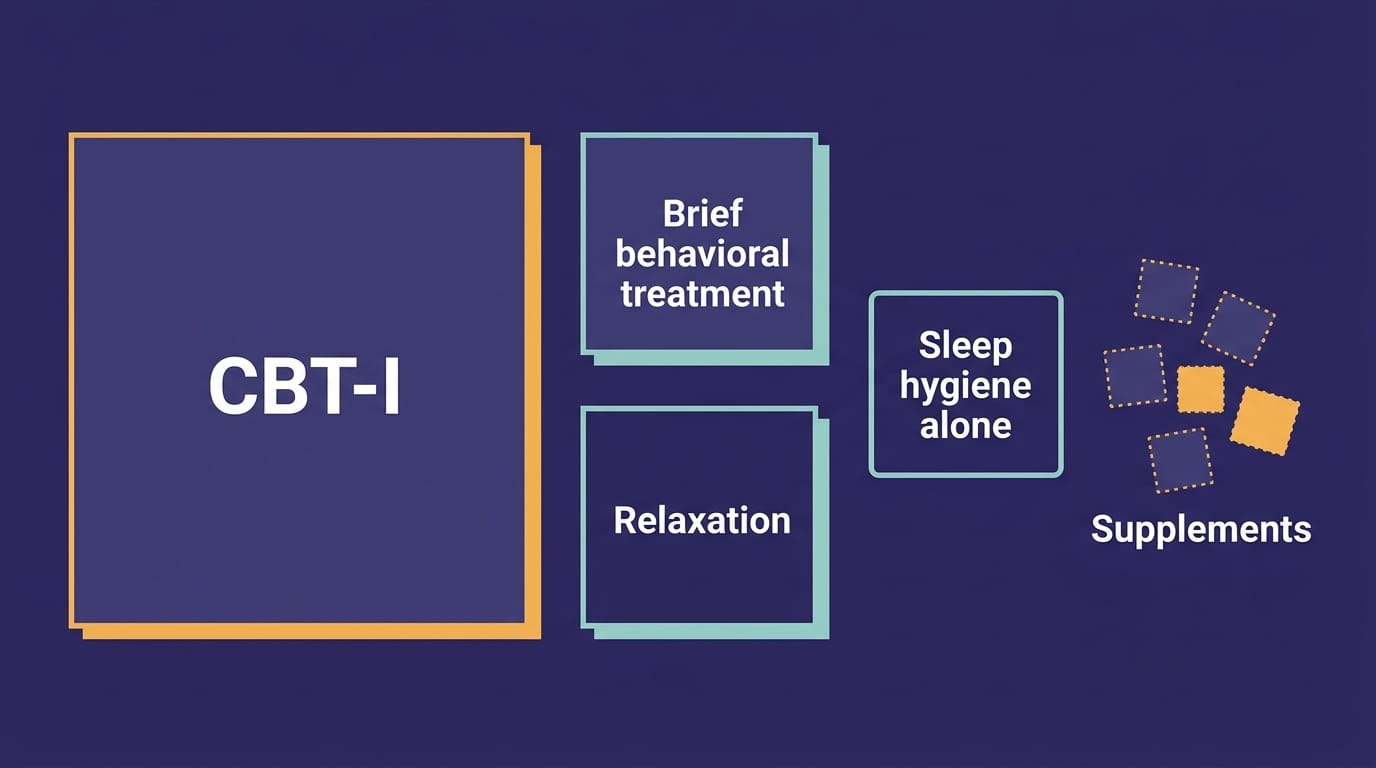
Among natural insomnia treatment options, structured CBT-I has a strong guideline recommendation for adults with chronic insomnia. Brief behavioral treatment and relaxation therapy have conditional recommendations. Sleep hygiene alone is not recommended as treatment. Several supplements have weak or insufficient evidence for chronic insomnia, so they sit at the uncertain end of the list.
These recommendations come from two guidelines. The 2025 VA/DoD guideline covers herbs, supplements and mind-body approaches. The American Academy of Sleep Medicine (AASM) guideline covers behavioral treatments.
| Option | Evidence position | What to know |
|---|---|---|
| CBT-I | Strong recommendation (AASM). Moderate overall evidence quality. | A structured therapy, not a list of tips. One part can leave you sleepier by day at first. |
| Brief behavioral treatment | Conditional recommendation. Moderate overall evidence quality. | A shorter option to ask about if full treatment is hard to reach. |
| Relaxation therapy | Conditional recommendation. Low overall evidence quality. | Benefits are modest. It can’t promise sleep on a given night. |
| Sleep hygiene alone | Conditional recommendation against using it alone. | Habits like a dark, quiet room still help as part of broader care. |
| Mindfulness, yoga, aerobic exercise | Insufficient evidence for or against (VA/DoD). | Yoga may improve sleep quality without necessarily treating insomnia. This isn’t advice against exercise. |
| Melatonin | VA/DoD weakly suggests against it for chronic insomnia. | It may help jet lag and delayed sleep-wake phase disorder, which are different problems. |
| Magnesium | Insufficient evidence for or against (VA/DoD). | A review in older adults found minimal evidence of benefit, at low to very-low certainty. |
| Valerian | VA/DoD weakly suggests against it for chronic insomnia. | Results have been inconsistent. |
| Chamomile | VA/DoD weakly suggests against it for chronic insomnia. | It can interact with medicines, including warfarin. |
| Ashwagandha | NCCIH says some preparations may help insomnia and stress. | Studies are small, preparations vary and long-term safety is uncertain. |
| Music | A Cochrane review found it may improve self-reported sleep quality. | Its effect on insomnia severity is uncertain. |
Read the table in three groups. CBT-I, brief behavioral treatment and relaxation therapy are the recommended treatments. Everyday habits, movement and music act as supports. They may help sleep feel better, but the evidence doesn’t show they treat insomnia. Supplements come last, and each needs its own safety check.
Want the whole picture on one page? The natural insomnia treatment mind map shows each branch and how they connect.
Why can sleep tips help without solving insomnia?
Sleep tips can help without solving insomnia because they aren’t the same as structured treatment. Sleep hygiene means everyday habits and bedroom conditions. The AASM conditionally recommends against using sleep hygiene alone for chronic insomnia. CBT-I is different: a structured therapy for sleep-related thoughts and habits.
None of this means your tips were wasted. Going to bed when you’re sleepy and getting up at the same time every day are NHS advice. So is keeping the bedroom dark and quiet.
The NHS calls insomnia long-term when it lasts 3 months or longer. At that point, habits are one part of care, not the whole plan. To learn what insomnia is and how it’s diagnosed, the insomnia guide covers the basics.
If light, noise or comfort is the sticking point, our sleep environment setup guide walks through practical fixes.
Good sleep habits and CBT-I are the same thing.
Habits alone aren’t recommended as treatment for chronic insomnia. CBT-I is a structured therapy for sleep-related thoughts and habits.
If every remedy failed, medication is the only route left.
Behavioral care is still a treatment option. The harder part is often finding it.
Natural means harmless.
Natural products can cause side effects and interact with medicines. NCCIH notes that natural doesn’t always mean safe.
So a bedtime routine that didn’t work doesn’t mean treatment has run out. It means the next step is a different kind of help.
At a glance
- CBT-I is structured treatment — it’s a therapy for sleep-related thoughts and habits, not a generic habit list.
- Brief treatment and relaxation have conditional recommendations — both are options to discuss, with different evidence quality.
- Supplement evidence and safety differ by ingredient — each product needs its own check.
- Access depends on your country and service — routes, costs and coverage vary.
What do CBT-I and brief behavioral treatment offer?
CBT-I is a structured therapy for sleep-related thoughts and habits. The AASM strongly recommends it for adults with chronic insomnia, and rates the overall evidence as moderate. Brief behavioral treatment is a shorter option with a conditional recommendation. Both are drug-free.
CBT-I has several parts, which is why the AASM calls it multicomponent. It isn’t one trick or one tip. A trained provider tailors the work to you.
Brief treatment is a shorter version. Ask about it if full treatment is hard to reach.
A patient fact sheet from Australia’s Sleep Health Foundation describes 4 to 8 sessions as usual. Programs vary. That’s a course length, not a promise of when sleep improves.
One step, sleep restriction, limits the time you spend in bed. It can raise daytime sleepiness at first. That’s one reason to do it with a clinician and not copy a schedule from the web.
Our CBT-I guide goes deeper into what the treatment involves.
CBT-I, with brief treatment as another option
CBT-I works on sleep-related thoughts and habits. The AASM strongly recommends it for adult chronic insomnia, with moderate overall evidence quality. Brief therapies have a conditional recommendation, also with moderate evidence quality.
A usual course runs 4 to 8 sessions, and programs vary. A clinician should set any limits on time in bed.
A video can show what text can’t. This Mayo Clinic video covers CBT-I in day-to-day practice.
Cognitive Behavioral Therapy for Insomnia in Day-To-Day Practice — Mayo Clinic
Can relaxation, mindfulness, yoga or exercise help?
Relaxation therapy has a conditional AASM recommendation as a stand-alone treatment, based on low-quality evidence. For mindfulness, yoga and exercise, VA/DoD finds insufficient evidence to recommend for or against them as chronic-insomnia treatment. Yoga may improve sleep quality without necessarily treating insomnia.
Relaxation therapy is a treatment option, but its benefits are modest. It can’t guarantee sleep on any given night.
“Insufficient evidence” doesn’t mean “don’t do it.” It isn’t advice against ordinary physical activity.
If you want to try mindfulness, our mindfulness for sleep guide explains the practice without treating it as a stand-in for CBT-I.
If worry about sleep is the main thing keeping you up, our guide to bedtime worry is a good next read.
A 2022 Cochrane review of music for insomnia shows why the difference between outcomes matters.
Did you know?
About 2.8 points: that’s how much music improved a sleep-quality score across 10 studies with 708 adults who had sleep difficulties, compared with no music or usual care. For insomnia severity, two studies with 63 adults showed no clear difference. The first result has moderate certainty. The second has very low certainty. You can see every figure, with who it applies to, on the statistics page.
Better-feeling sleep and less insomnia are two different results. Supportive benefits can be real. They just answer a different question from “is my insomnia treated?”
What does the evidence say about natural sleep supplements?
Natural sleep aids have weak or uncertain evidence for chronic insomnia, and safety differs by product. VA/DoD weakly suggests against melatonin, valerian and chamomile for it, and finds insufficient evidence for magnesium. Some ashwagandha preparations may help, but long-term safety is unclear. Natural doesn’t always mean safe.
If you’ve spent a lot of money on natural sleep aids, that frustration makes sense. The evidence below helps you decide what is worth asking about before you spend more.
The table draws on a 2021 review of magnesium in older adults and NCCIH’s ashwagandha page, plus the VA/DoD guideline.
| Ingredient | Evidence for chronic insomnia | Safety to know |
|---|---|---|
| Melatonin | VA/DoD weakly suggests against it for chronic insomnia. NCCIH says it may help jet lag and delayed sleep-wake phase disorder, which are different problems. | |
| Magnesium | VA/DoD finds insufficient evidence for or against it. In two small trials with 55 older adults, it shortened time to fall asleep by about 17 minutes compared with an inactive treatment (placebo). The range ran from about 7 to 27 minutes, and certainty was low. Total sleep time showed no clear gain. | Kidney problems raise the risk of too much magnesium. High doses can cause diarrhea, nausea and cramps. It can interact with some medicines, including certain antibiotics. |
| Valerian | VA/DoD weakly suggests against it for chronic insomnia. NCCIH reports inconsistent results. | Herbs can interact with medicines, so show a pharmacist your list. |
| Chamomile | VA/DoD weakly suggests against it for chronic insomnia. | It can interact with medicines, including warfarin. If you’re allergic to related plants such as ragweed, check first. |
| Ashwagandha | NCCIH says some preparations may help insomnia and stress. Studies are small, and preparations vary. | Long-term safety is uncertain. Avoid it during pregnancy, and don’t use it while breastfeeding. Liver injury has been reported, so discuss it first if you have health problems. |
VA/DoD goes further for two products. It recommends against kava for chronic insomnia and weakly suggests against cannabis or its derivatives.
A cup of tea as a bedtime ritual and a concentrated supplement are not the same thing. Don’t judge one by the other.
Before you buy anything, ask three things. What was it studied for? What does the evidence say about chronic insomnia? Could it clash with my medicines or health conditions?
Looking for another ingredient, such as CBD, tea or a magnesium form? The natural insomnia treatment questions page answers them one by one.
Can drug-free care fit alongside prescribed treatment?
Drug-free care can fit alongside prescribed treatment, and choosing it doesn’t mean medication is wrong. The 2026 AASM guideline conditionally suggests CBT-I plus medication over medication alone. It also conditionally suggests against routinely choosing the combination over CBT-I alone. Evidence certainty is low, so personal preference matters.
If you already take a prescribed medicine, don’t stop or change it on your own. Talk with the person who prescribed it. The 2026 AASM guideline on combination treatment is a useful starting point for that talk.
You can say it plainly: “I’d like to avoid sleeping pills if possible. What behavioral options are there?” Taking a prescribed medicine isn’t a failure, and wanting drug-free care isn’t a demand to stop it.
Want to turn your preference into questions you can bring to a visit?
Build printable notes for your appointmentTreatment discussion planner builds printable notes for an insomnia appointment.When should a clinician help you choose treatment?
A clinician should help you choose treatment when you’ve had trouble sleeping for months, when daily life feels hard to cope with, or when certain health conditions are present. Some conditions mean behavioral treatment needs adapting or delaying. Supplements need a check against your health conditions and medicines too.
Book an appointment if
- Months of poor sleep. Trouble sleeping for months, or sleep that makes daily life hard to cope with, is a reason to see a GP or primary-care clinician.
- Sleepiness while driving. Don’t drive when you feel sleepy.
- Loud snoring or gasping in sleep. Ask a clinician about possible sleep apnea. Our sleep apnea guide covers these snoring and gasping concerns.
Conditions that can change how CBT-I is done
The VA/DoD provider summary lists these conditions. Behavioral treatment may need adapting or delaying if any apply. A clinician should decide that, not an app or a web page.
- Medically unstable. Treatment may need to wait until you’ve been assessed.
- Active alcohol or drug use disorder. A clinician should assess you before treatment, and the guideline identifies a delay.
- Excessive daytime sleepiness. Talk with your treating clinician about adapting or delaying treatment.
- Fall risk at night, or trouble moving into or out of bed. A clinician can adapt treatment for you.
- Exposure-based PTSD treatment. Care needs coordinating, and the guideline identifies a delay.
- Uncontrolled seizure disorder. A clinician should assess you before treatment, and the guideline identifies a delay.
- Bipolar disorder. A clinician can adapt behavioral treatment.
- Pregnancy or postpartum insomnia. Discuss an adapted approach with a clinician.
Check products before you use them
Natural doesn’t always mean safe. Magnesium, ashwagandha and chamomile each have limits, and the ingredient table above lists each one. Tell your clinician or pharmacist about every product and medicine you use.
Current acute mental-health symptoms need prompt clinical assessment. If you’re in crisis or in immediate danger, use the route for your country.
If you need urgent help
- US — Call, text or chat with the 988 Suicide & Crisis Lifeline if you’re in emotional distress or a mental-health crisis.
- UK — If you can’t keep yourself or someone else safe, call 999 or go to A&E now.
- Canada — If you’re thinking about suicide, call or text 9-8-8. For immediate danger, call 9-1-1.
- Australia — For an emergency, call 000. Lifeline on 13 11 14 offers crisis support.
How can you find drug-free insomnia treatment?
You have several routes to drug-free insomnia treatment. Which one fits depends on your country and the service. Some are free, some depend on insurance or a doctor’s plan, and costs vary. Check cost before booking, and bring a list of everything you’ve tried.
| Country | Where to start | Cost and coverage |
|---|---|---|
| US | The Society of Behavioral Sleep Medicine directory lists behavioral sleep providers. Phone or video appointments may be available. Insomnia Coach is a free self-care app. CBT-i Coach is meant for use with a provider. | Check whether your insurance covers the treatment before you book. |
| UK | A GP may offer face-to-face therapy or an online self-help program for insomnia. | NHS CBT is free for many mental-health problems. Insomnia-specific availability needs a local check, and waiting times vary. |
| Canada | Sleepwell points to selected CBT-I books, apps and websites. | Psychotherapy isn’t universally publicly funded, so ask about cost. |
| Australia | Trained psychologists may provide CBT-I in person or by telehealth, and a GP can help you find a service. Medicare Mental Health lists a free online Insomnia Program based on CBT. | A GP mental health treatment plan may give a Medicare route. Confirm your eligibility and any gap fees. |
The US routes come from Mayo Clinic’s guide to CBT instead of sleeping pills.
Tell every provider which complementary products or approaches you use. A few questions can make the visit more useful:
- Which behavioral treatments do you offer, and is a shorter program available?
- Does anything in my health history change how treatment should be done?
- How will we judge whether it’s helping?
- How will I pay for it?
To gather all this on one page, the Treatment discussion planner builds printable notes for an insomnia appointment.
How should you review progress and reconsider an approach?
Review progress by tracking how you sleep and how the problem affects your days, then take those notes to your provider. A sleep diary can help track sleep patterns and treatment progress. If problems persist, ask for reassessment. A provider can review whether the approach and format fit your situation.
Feeling like your sleep is broken is understandable after many tries. A setback is a reason to review the plan with your provider.
A worked example
Picture an adult who has tried blackout curtains, a bedtime routine and several supplements. Sleep is still hard, and work is suffering. A useful next step could look like this:
- Write down what’s been tried. Include every product and medicine.
- Book an appointment. Trouble for months, or difficulty coping, is the cue.
- Ask about behavioral treatment. Raise CBT-I and brief options.
- Check the payment route. Use the access table above for your country.
Nothing in this example predicts how much sleep will improve.
Study numbers are averages, and they don’t forecast your own results. A 2016 review of online CBT-I programs found that improvements in selected measures lasted at follow-up, from 4 to 48 weeks. Those were older programs, and the finding isn’t a promise for any current app.
The natural insomnia treatment statistics page shows what each number measured and for whom.
Key takeaways
- Remember — Habits support sleep, but CBT-I is the drug-free option with a strong recommendation.
- Do — List what you’ve tried, including every product and medicine, and ask a provider about behavioral treatment.
- If it continues — Book an appointment if sleep trouble lasts for months or makes daily life hard to cope with.
Know which step to take next
The natural insomnia treatment Sleep Compass points you to the section that fits what you’ve tried. More in Sleep Disorders.
Find your starting point →Natural insomnia treatment questions
How long does CBT-I usually take?
A usual CBT-I course lasts 4 to 8 sessions. That figure comes from an Australian patient fact sheet. Programs vary, so ask your provider how long their program runs. A course length isn’t a promise of when your sleep will improve.
Want to know what the treatment involves? Our CBT-I guide explains it in more depth.
What should I bring to an insomnia appointment?
For an insomnia appointment, bring a short account of your sleep problem, the approaches you’ve already tried and every complementary product you use. Tell your providers about supplements and herbal products too, since some interact with medicines. Existing sleep notes, such as a sleep diary, can help the discussion.
Which natural sleep supplement should I choose?
No natural sleep supplement has been shown to work for everyone with insomnia. VA/DoD weakly suggests against several for chronic insomnia and finds the magnesium evidence insufficient. CBT-I, a therapy rather than a supplement, is the drug-free option with a strong recommendation. Purpose, evidence and safety matter more than a “natural” label.
Can I use a free insomnia app without a therapist?
Insomnia Coach is a free, publicly available education and self-care app from the VA National Center for PTSD. You can use it without a therapist. CBT-i Coach is a different app meant for use with a provider, not for self-care. If any condition in the safety list above applies, check with a clinician first.
Is CBT-I covered by insurance or public health care?
CBT-I coverage depends on where you live and on the service. US readers should check with their insurance before booking. In the UK, NHS availability for insomnia needs a local check. Canada doesn’t publicly fund all psychotherapy. Australian readers should confirm Medicare eligibility and any gap fees.
Can I take herbs with prescribed medicines?
Some herbs and supplements interact with medicines, so a pharmacist or clinician should check them against your actual medicine list. Chamomile can interact with warfarin, and magnesium can interact with certain antibiotics. Don’t assume a natural product is safe with your prescriptions.
Can I get behavioral sleep treatment by video?
Some providers offer behavioral sleep treatment by phone or video. In the US, phone or video appointments may be available, and in Australia trained psychologists may offer CBT-I by telehealth. Ask the service whether it can see you where you live.
Sources
- Buysse et al., Journal of Clinical Sleep Medicine, 2026 (DOI: 10.1007/s44470-025-00038-8). Supports: the position on combining CBT-I with medication.
- VA/DoD, Chronic Insomnia Disorder and Obstructive Sleep Apnea Clinical Practice Guideline, 2025. Supports: recommendations on herbs, supplements, kava, cannabis, mindfulness, yoga and exercise.
- Edinger et al., Journal of Clinical Sleep Medicine, 2021 (DOI: 10.5664/jcsm.8986). Supports: recommendations on CBT-I, brief therapy, relaxation and sleep hygiene alone, and sleepiness with sleep restriction.
- VA/DoD, Chronic Insomnia Disorder and Obstructive Sleep Apnea Provider Summary, 2025. Supports: conditions that need adapted or delayed behavioral treatment.
- NCCIH, Sleep Disorders and Complementary Health Approaches: Usefulness and Safety, n.d. (accessed October 11, 2026). Supports: yoga and sleep quality, valerian results, snoring and gasping, telling providers about products.
- Mah and Pitre, BMC Complementary Medicine and Therapies, 2021 (DOI: 10.1186/s12906-021-03297-z). Supports: magnesium in older adults.
- Office of Dietary Supplements, Magnesium: Fact Sheet for Health Professionals, 2026. Supports: magnesium safety and interactions.
- NCCIH, Melatonin: What You Need To Know, n.d. (accessed October 11, 2026). Supports: melatonin and jet lag or delayed sleep-wake phase disorder.
- NCCIH, Ashwagandha: Usefulness and Safety, 2023. Supports: ashwagandha evidence, long-term safety, pregnancy and liver injury.
- NCCIH, Chamomile: Usefulness and Safety, n.d. (accessed October 11, 2026). Supports: chamomile interactions and allergy.
- Seyffert et al., PLOS ONE, 2016 (DOI: 10.1371/journal.pone.0149139). Supports: online CBT-I improvements at follow-up.
- Jespersen et al., Cochrane Database of Systematic Reviews, 2022 (DOI: 10.1002/14651858.CD010459.pub3). Supports: music, sleep quality and insomnia severity.
- NHS, Insomnia, 2024. Supports: self-help habits, long-term insomnia, when to see a GP, sleepy driving, UK routes.
- VA National Center for PTSD, Insomnia Coach, 2026. Supports: the Insomnia Coach app.
- VA Mobile, CBT-i Coach, n.d. (accessed October 11, 2026). Supports: the CBT-i Coach app.
- NHS, Cognitive behavioural therapy (CBT), n.d. (accessed October 11, 2026). Supports: NHS CBT availability and waiting times.
- Medicare Mental Health, Insomnia Program, n.d. (accessed October 11, 2026). Supports: the free Australian online insomnia program.
- Public Health Agency of Canada, Inequalities in mental health, well-being and wellness in Canada, 2024. Supports: psychotherapy funding in Canada.
- 988 Suicide & Crisis Lifeline, 988 Lifeline, n.d. (accessed October 11, 2026). Supports: US crisis support.
- NHS, Where to get urgent help for mental health, n.d. (accessed October 11, 2026). Supports: UK urgent help.
- Public Health Agency of Canada, Mental health support: Get help, 2026. Supports: Canadian crisis support.
- healthdirect Australia, Mental health helplines, n.d. (accessed October 11, 2026). Supports: Australian crisis support.
- Mayo Clinic, Insomnia treatment: Cognitive behavioral therapy instead of sleeping pills, 2023. Supports: US provider directory, insurance check, phone or video sessions.
- Sleep Health Foundation, Cognitive Behavioural Therapy for Insomnia (CBT-I), 2025. Supports: usual session count, sleep diary, Australian routes.
- Sleepwell, CBTi, n.d. (accessed October 11, 2026). Supports: Canadian CBT-I starting resources.
Sources checked · Next review
How we made this guide: researched from the sources above, drafted with AI assistance and edited by Aamir Bashir, Founder & Editor. Read our editorial policy.



